European Journal of Medical Case Reports
Volume 10(5):154–163
Transanal endorectal pull-through for hirschsprung disease: optimizing outcomes, reducing complications, and strengthening surgical care in resource-limited settings
Mathayo Shadrack1,2,3* , Alex Mashaka1,4,5, Mohammed Sultan Salim1,2,4, Ally Hamisi Mwanga1,2,4, Zaitun Bokhary1,2,4
Correspondence to: Mathayo Shadrack
*Muhimbili University of Health and Allied Sciences (MUHAS), Dar es Salaam, Tanzania.
Email: shadrackmathew@gmail.com
Full list of author information is available at the end of the article.
Received: 29 November 2025 | Revised (1): 02 January 2026 | Accepted: 27 February 2026
ABSTRACT
Background:
Hirschsprung’s disease (HD) is a congenital absence of enteric-ganglion cells causing distal bowel obstruction, chronic constipation, and progressive proximal colonic dilatation. In resource-limited-settings, delayed presentation and limited pathology support often necessitate multistage-surgery, increasing morbidity, caregiver burden, and healthcare costs. Single-stage transanal endorectal pull-through (TAPT) offers a minimally invasive alternative that avoids laparotomy and colostomy.
Methods:
This mixed prospective–retrospective case series included eight children aged 2.5–9 years with rectosigmoid-HD who underwent single-stage TAPT between September 2024 and July 2025. Preoperative optimization involved regular rectal irrigations, nutritional rehabilitation, intravenous antibiotics, and correction of fluid and electrolyte imbalance. Diagnosis was established using contrast-enema and full-thickness rectal biopsy. TAPT was performed without intraoperative frozen section analysis. Outcomes assessed included time to first stool, stool-frequency, continence, Hirschsprung-associated enterocolitis (HAEC), anastomotic complications, weight-gain, and early quality-of-life indicators.
Results:
All patients presented with long-standing constipation and abdominal distension. The median-length of resected bowel was 20 cm. Time to first stool ranged from 24 to 48 hours. One patient (12.5%) developed mild HAEC, which resolved with conservative management. No anastomotic leaks, strictures, or fecal incontinence occurred. At a median follow-up of 4 months (range 3–6 months), all patients passed 1 to 2 soft-stools daily, demonstrated improved weight-gain, and achieved age-appropriate-continence based on clinical assessment and parental reporting.
Conclusion:
TAPT is a safe, effective, and reproducible strategy for rectosigmoid-HD in resource-limited-settings. Even without frozen section support and despite delayed presentation, it achieves excellent early functional outcomes, minimal morbidity, reduced hospitalization, and lower caregiver and healthcare-burden.
Keywords:
Hirschsprung’s disease, transanal endorectal pull-through, rectosigmoid aganglionosis, pediatric surgery, resource-limited settings.
Background
Hirschsprung’s disease (HD) is a congenital disorder characterized by the absence of neural crest-derived enteric ganglion cells in the distal bowel, resulting in tonic contraction, functional obstruction, and progressive proximal bowel dilatation [1]. The global incidence ranges from 1 in 4,000 to 7,000 live births, with a recognized male predominance [2]. While most cases present in the neonatal period with delayed passage of meconium, late presentation beyond infancy is common in resource-limited settings due to inadequate diagnostic capacity, limited community awareness, and a shortage of trained pediatric surgeons [3]. These delays often lead to chronic constipation, recurrent abdominal distension, failure to thrive, and an increased risk of Hirschsprung-associated enterocolitis (HAEC).
Historically, management of HD relied on multistage procedures involving an initial diverting colostomy, followed by abdominal pull-through and subsequent stoma closure [4]. Although effective, staged surgery is associated with stoma-related complications, repeated hospitalizations, electrolyte disturbances, multiple anesthetic exposures, and significant psychosocial and financial strain on caregivers’ burdens that are amplified in low-income settings. The introduction of the transanal endorectal pull-through (TAPT) by De la Torre in 1998 marked a paradigm shift toward minimally invasive, single-stage repair without laparotomy [5]. TAPT has been associated with reduced postoperative pain, faster recovery, shorter hospital stays, improved cosmesis, and lower overall cost compared with traditional multistage approaches [6,7].
Despite strong evidence supporting TAPT, its adoption in low-resource environments is sometimes limited by the unavailability of intraoperative frozen section analysis, inconsistent access to pediatric anesthesia, and imaging constraints. Frozen section services are often unavailable due to the lack of cryostat equipment, trained histotechnologists, and on-site pathology support, as well as costs related to equipment maintenance and specimen processing. In such contexts, surgeons must rely on careful intraoperative assessment of bowel caliber, wall thickness, peristalsis, and vascularity to identify the transition zone [8,9]. This study presents a series of eight children with rectosigmoid HD managed with single-stage TAPT, highlighting operative decision-making, diagnostic challenges, and early outcomes in a resource-constrained setting.
Methods
Study design and ethics
This mixed prospective–retrospective study included all children who underwent single-stage TAPT between September 2024 and July 2025 at a tertiary referral hospital. Ethical approval covered both retrospective chart review and prospective follow-up. Written informed consent was obtained from parents or legal guardians for participation and publication.
Eligibility criteria
Inclusion criteria
- Rectosigmoid HD confirmed by contrast enema and full-thickness rectal biopsy.
- Single-stage TAPT as primary surgical management.
- Minimum postoperative follow-up of 3 months.
Exclusion criteria
Long-segment HD, total colonic aganglionosis, prior colostomy, or incomplete medical records.
Preoperative management
All patients underwent standardized preoperative optimization, including twice-daily saline rectal irrigations, nutritional rehabilitation, intravenous ceftriaxone and metronidazole, analgesia, and correction of fluid and electrolyte abnormalities, in line with established pediatric surgical care principles [10]. Baseline laboratory investigations and contrast enema imaging were used to assess bowel dilatation and identify the transition zone.
Surgical technique
A Soave-type TAPT was performed as originally described by De la Torre [5]. Perineal exposure was achieved using a Lone Star retractor. A circumferential mucosal incision was made approximately 1 cm above the dentate line, followed by submucosal dissection to create a mucosal sleeve. Full-thickness mobilization proceeded proximally. In the absence of frozen section analysis, the transition zone was identified intraoperatively based on improvement in bowel caliber, thinning of the bowel wall, restoration of normal vascular pattern, and improved peristalsis. Resection was continued proximally until clearly healthy, ganglionated bowel was reached, ensuring a tension-free pull-through. A coloanal anastomosis was performed using absorbable sutures.
Postoperative follow-up
Patients were reviewed at 1 week, 1 month, 3 months, and 6 months postoperatively. Follow-up assessments included stool frequency, continence status (clinical assessment and parental reporting), HAEC episodes, anastomotic complications, weight progression, and caregiver-reported quality-of-life indicators.
Results
Demographics and clinical features
Eight children (5 males, 3 females) aged 2.5 to 9 years were included. All presented with long-standing constipation and recurrent abdominal distension. Contrast enema demonstrated a rectosigmoid transition zone in every patient.
Perioperative outcomes
The median length of resected bowel was 20 cm (range, 9–40 cm). Time to first postoperative stool ranged from 24 to 48 hours. One patient (12.5%) developed mild HAEC, which resolved with antibiotics and rectal irrigations. No anastomotic leaks, strictures, or reoperations occurred. Median hospital stay was 5 days.
Functional outcomes
At a median follow-up of 4 months (range 3–6 months), all patients passed 1–2 soft stools daily. Continence was age-appropriate in all children, with no episodes of soiling reported. All patients demonstrated clinical improvement in weight and nutritional status, and none had persistent constipation.
Case Presentations
Case 1
A 5-year-old girl presented with a two-year history of progressive abdominal distension and refractory constipation requiring frequent enemas. Plain abdominal radiography demonstrated grossly dilated bowel loops with multiple air–fluid levels. Contrast enema revealed a narrowed rectum with a rectosigmoid transition zone and markedly dilated proximal colon (Figure 1A and B). Full-thickness rectal biopsy confirmed aganglionosis.
Perineal exposure was achieved using a Lone Star retractor, facilitating safe transanal dissection (Figure 2).
Single-stage TAPT was performed with resection of 40 cm of aganglionic bowel followed by coloanal anastomosis. She passed stool within 36 hours, tolerated feeds on postoperative day 2, and was discharged on day 5. At 3-month follow-up, she passed 1–2 formed stools daily without soiling or HAEC.
Case 2
A 3-year-old boy presented with abdominal distension, poor growth, and recurrent vomiting. Imaging demonstrated proximal colonic dilatation with a narrow rectosigmoid segment. Full-thickness rectal biopsy confirmed Hirschsprung disease. TAPT was performed uneventfully, with 18 cm of bowel resected (Figure 3).
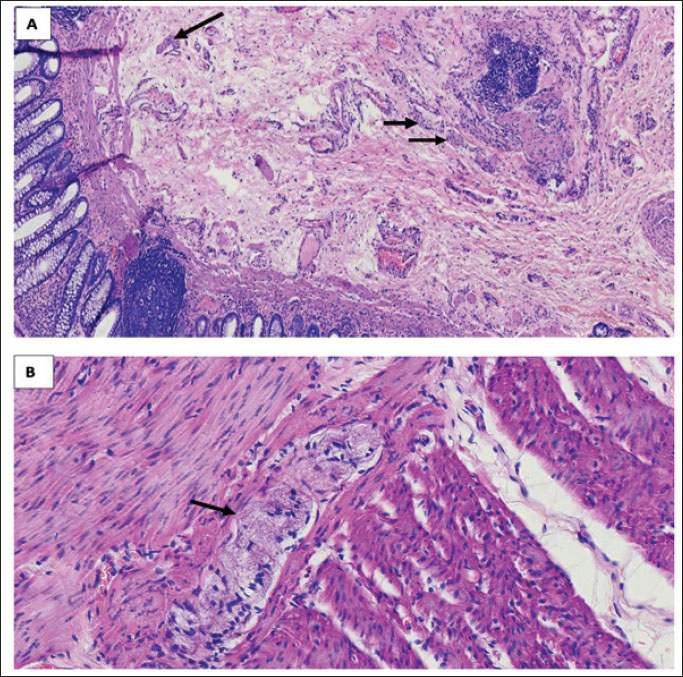
Figure 1. (A) Plain abdominal radiograph demonstrates grossly dilated bowel loops with multiple air-fluid levels, highly suggestive of distal intestinal obstruction. Contrast (barium) enema outlines a rectosigmoid transition zone (black arrow) with markedly dilated proximal bowel (black star).
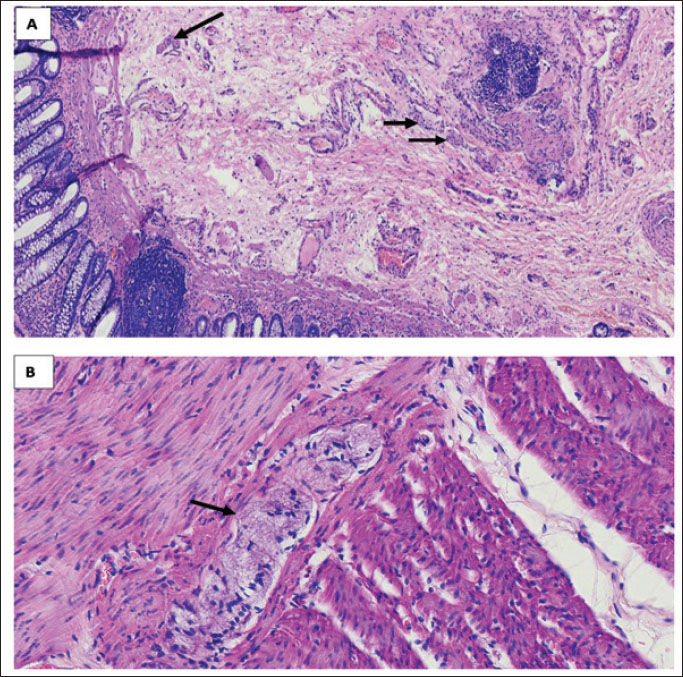
Figure 2. The Lone Star retractor was strategically applied to provide optimal exposure of the anal canal (black arrows), thereby facilitating clear visualization and enabling a meticulous, safe, and controlled transanal dissection with minimal tissue handling and improved precision.
The patient resumed stooling within 30 hours and oral feeding by postoperative day three. At four-month follow-up, he passed soft stools twice daily with normal continence and no episodes of HAEC.
Case 3
A 9-year-old boy with longstanding constipation, failure to thrive, and megacolon on imaging underwent bowel optimization prior to surgery. TAPT was performed with resection of approximately 22 cm of diseased bowel, followed by coloanal anastomosis approximately 2.5 cm above the dentate line (Figure 4A and B).
He passed stool on postoperative day two and demonstrated significant weight gain during follow-up. At 4 months, continence was normal, and nutritional status had markedly improved.
Case 4
A 2.5-year-old girl presented with chronic constipation requiring repeated enemas. Contrast enema demonstrated a distinct rectosigmoid transition zone (Figure 5). TAPT was performed with resection of 20 cm of aganglionic bowel.
She passed stool within 24 hours postoperatively and had an uncomplicated recovery. At the 3-month follow-up, she had no abdominal distension, constipation, or HAEC.
Case 5
A 7-year-old boy presented with severe constipation affecting school performance and psychosocial well-being. Imaging confirmed rectosigmoid Hirschsprung disease. TAPT was performed with resection of 16 cm of bowel and coloanal anastomosis (Figure 6).
He resumed bowel movements within 28 hours and was discharged on postoperative day four. At follow-up, stool frequency normalized, continence was preserved, and quality of life improved substantially.
Case 6
A 4-year-old boy presented with recurrent abdominal distension and poor appetite. TAPT was performed with resection of 9 cm of aganglionic bowel. Postoperatively, he developed mild HAEC on day four, presenting with fever and foul-smelling diarrhea. This resolved with intravenous antibiotics and rectal irrigations.
At 4-month follow-up, he maintained normal bowel habits with no recurrent enterocolitis.
Case 7
A 5-year-old girl presented with a three-year history of constipation, abdominal bloating, and recurrent emergency visits. Contrast enema suggested a rectosigmoid transition zone (Figure 7). TAPT was performed with resection of 32 cm of bowel.
She passed stool within 24 hours and had an uncomplicated postoperative course. At 3 months, she passed 1 to 2 soft stools daily, with improved appetite and normal continence.
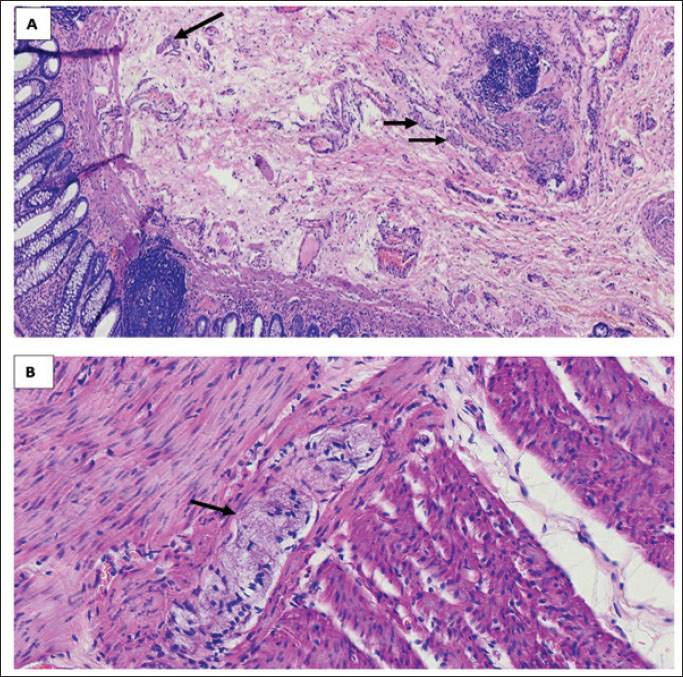
Figure 3. Illustrating a successful mucosectomy, followed by submucosal and muscular dissection to mobilize the rectosigmoid colon. Gross inspection and tapering of the transition segment (black arrows) guided the resection margin in the absence of frozen section capability
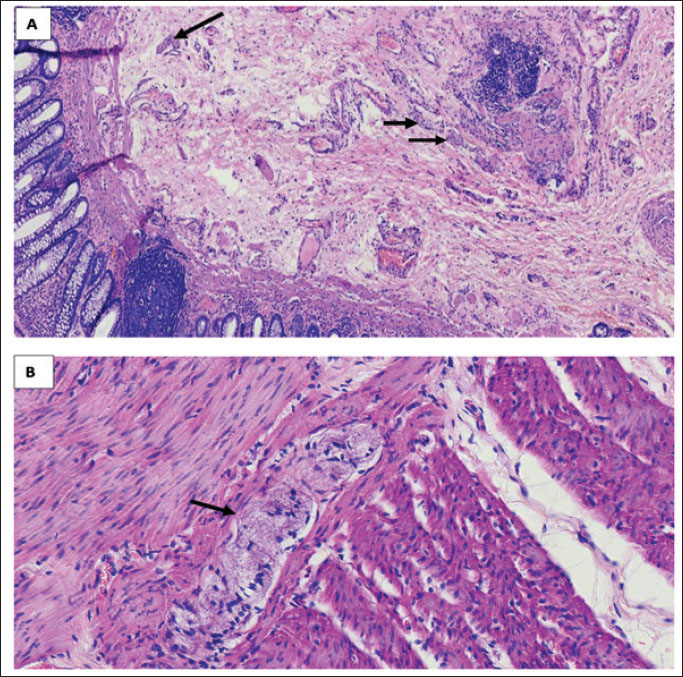
Figure 4. (A) illustrates the transanal pull-through extended up to the sigmoid colon, guided by the transition zone to ensure healthy ganglionated bowel (blue arrow). The aganglionic segment was resected, followed by a coloanal anastomosis (black arrow).
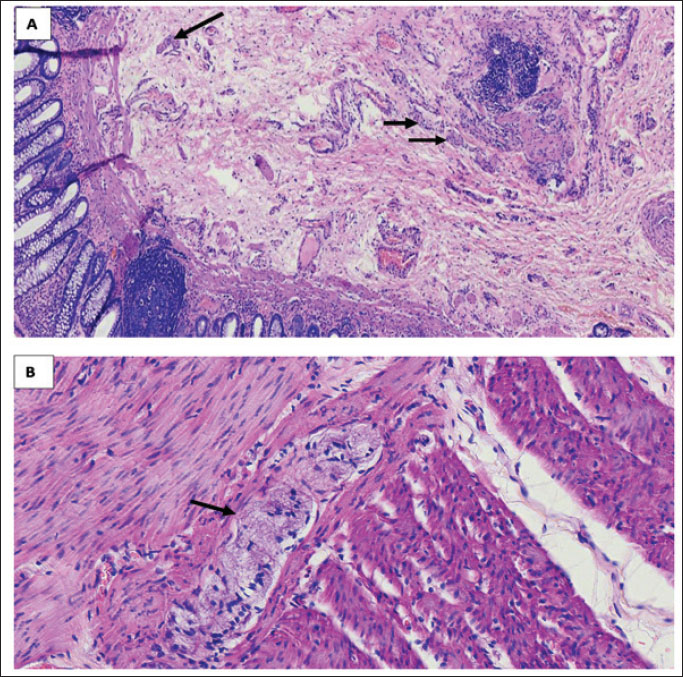
Figure 5. Contrast enema demonstrates a distinct transition zone at the rectosigmoid colon (black arrows), with contrast freely advancing into the dilated proximal colon, highlighting the narrowed aganglionic segment and assisting in diagnosis and preoperative surgical planning.
Case 8
A 7-year-old boy presented with chronic constipation, recurrent fecal impaction, and frequent school absenteeism. Radiologic evaluation confirmed rectosigmoid Hirschsprung disease (Figure 8). TAPT was performed with resection of 36 cm of bowel.
He resumed bowel movements within 30 hours and tolerated oral intake well. At 4-month follow-up, stooling was consistent, continence was excellent, and psychosocial functioning improved significantly.
Pathologic findings
Histopathology confirmed aganglionosis with hypertrophic nerve bundles in all resected segments. All proximal margins contained normal ganglion cells (Figure 9A, B).
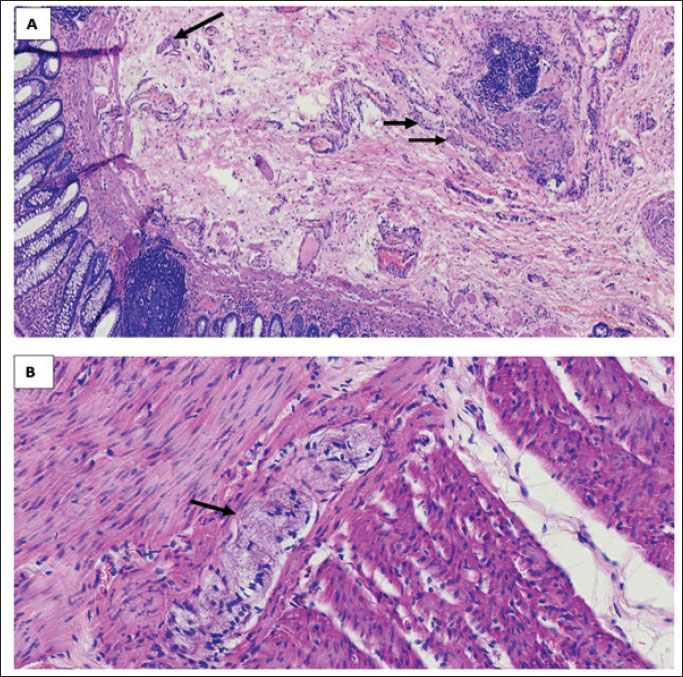
Figure 6. Transanal pull-through with coloanal anastomosis. The mobilized bowel was gently delivered through the anal canal and anastomosed to the anoderm using interrupted absorbable sutures (black arrow), ensuring mucosal apposition and tension-free repair.
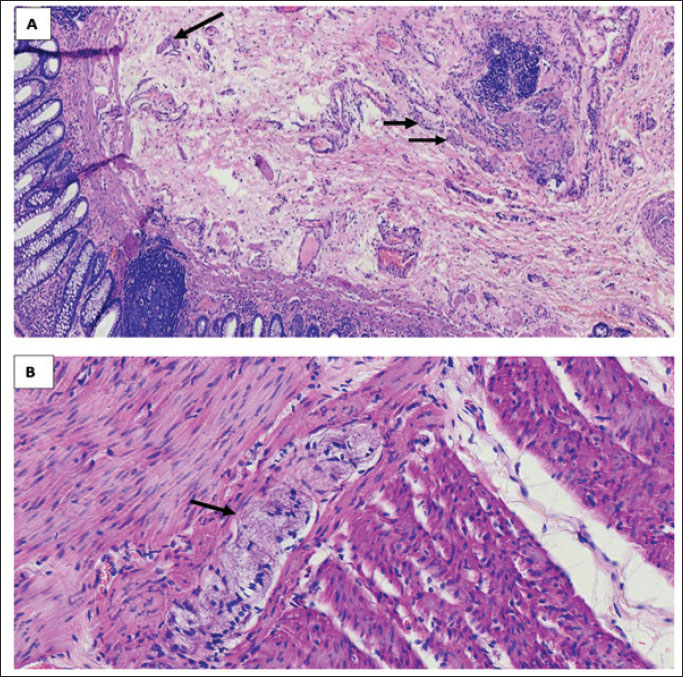
Figure 7. Contrast enema demonstrates a distinct transition zone at the sigmoid colon (black arrow), with proximal bowel dilation, raising strong suspicion for Hirschsprung’s disease and providing crucial radiologic guidance for surgical planning and confirmation of the affected segment.
Discussion
This series demonstrates that single-stage TAPT is safe and effective for rectosigmoid HD in resource-limited settings, even in the context of late presentation and absence of frozen section analysis. Delayed diagnosis observed in this cohort mirrors reports from similar regions, where limited pediatric surgical expertise and diagnostic infrastructure remain significant challenges [1,3,6].
Early functional outcomes in this study are comparable to international reports supporting TAPT as a reliable alternative to staged procedures [6-8]. Despite the lack of intraoperative pathology, all patients achieved satisfactory outcomes, reinforcing evidence that meticulous intraoperative assessment of bowel characteristics can reliably guide resection [9-11]. Concerns regarding residual aganglionosis remain valid; however, careful surgical judgment and postoperative histopathologic confirmation mitigated this risk in our series Table 1.
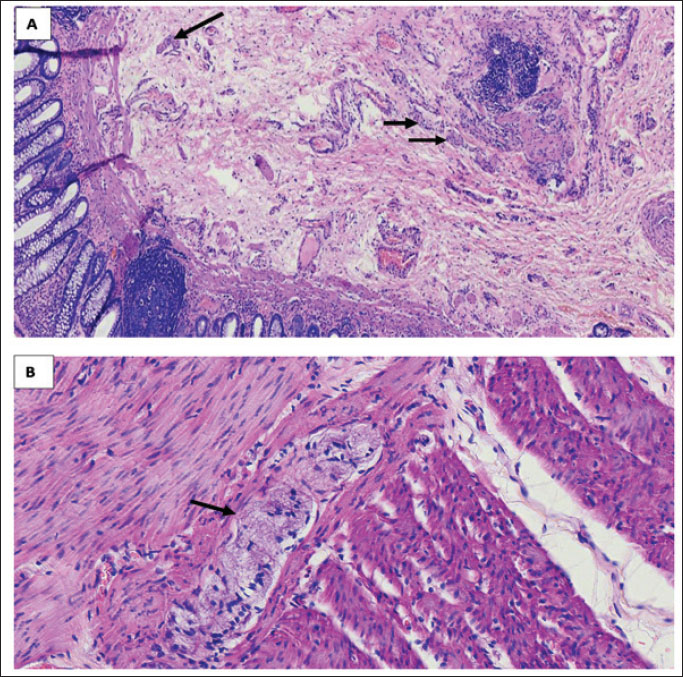
Figure 8. Illustrates the diseased segment of the rectum and sigmoid colon with a distinct transition zone (black arrows). The aganglionic segment was carefully resected, and a transanal pull-through was completed up to the proximal sigmoid to ensure healthy bowel margins.
Table 1. Summary of patient characteristics and surgical outcomes following transanal endorectal pull-through (TAPT).
| VARIABLE | RESULT |
|---|---|
| Number of patients (N) | 8 |
| Sex distribution (Male : Female) | 5: 3 |
| Age at surgery (years) | 2.5–9 years |
| Type of Hirschsprung disease | Rectosigmoid aganglionosis (100%) |
| Common presenting symptoms | Chronic constipation and abdominal distension (100%) |
| Diagnostic modalities | Contrast enema and full-thickness rectal biopsy |
| Preoperative optimization | Rectal irrigations, nutritional rehabilitation, IV antibiotics, fluid–electrolyte correction |
| Surgical approach | Single-stage transanal endorectal pull-through (Soave-type) |
| Intraoperative frozen section | Not available |
| Median length of resected bowel (cm) | 20 cm (range: 9–40 cm) |
| Intraoperative complications | None |
| Time to first postoperative stool | 24–48 hours |
| Median length of hospital stay | 5 days |
| Hirschsprung-associated enterocolitis (HAEC) | 1 patient (12.5%), mild, treated conservatively |
| Anastomotic leak | 0 |
| Anastomotic stricture | 0 |
| Fecal incontinence | 0 |
| Stool frequency at follow-up | 1–2 soft stools/day |
| Continence at 3–6 months | Normal continence in all patients (100%) |
| Nutritional outcome | Improved weight gain in all patients |
| Follow-up duration | 3–6 months |
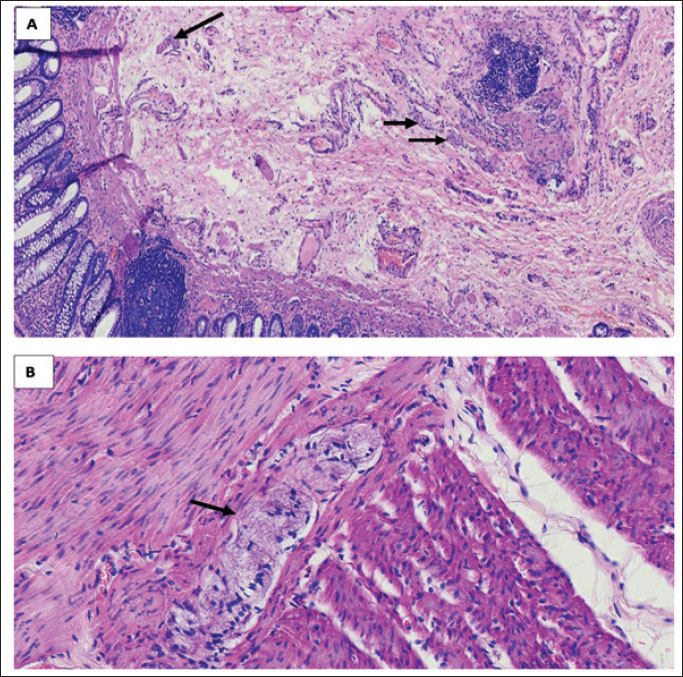
Figure 9. Hematoxylin and Eosin-stained sections of aganglionic rectal segment: A &B show aganglionic rectal segment in a child with Hirschsprung disease, ganglion cells are absent, and hypertrophic nerves are identified in submucosal and myenteric plexus, as indicated by black arrows (A x100 magnification, B x400 magnifications).
The observed HAEC rate of 12.5% aligns with globally reported rates ranging from 10% to 20% [12]. Notably, no anastomotic strictures, leaks, or fecal incontinence were encountered, consistent with outcomes reported in older children undergoing TAPT [13-15]. Beyond clinical outcomes, several patients demonstrated marked psychosocial improvement, including improved school attendance, appetite, and social confidence, which are particularly meaningful in low-resource environments.
Limitations
The small sample size limits generalizability and precluded subgroup analysis based on age or severity of megacolon. Follow-up was limited to six months, preventing assessment of long-term continence outcomes. The single-center design may introduce selection bias. Objective continence scoring systems were not used, relying instead on clinical assessment and parental reporting.
Conclusion
Single-stage TAPT is a safe, effective, and feasible approach for managing rectosigmoid Hirschsprung disease in resource-limited settings. Despite delayed presentation and absence of frozen section support, excellent early functional outcomes with minimal morbidity were achieved. TAPT should be considered the preferred first-line surgical option in similar environments, with future studies focusing on long-term functional and quality-of-life outcomes.
Process guideline
This case series has been reported in accordance with the PROCESS 2025 criteria [16].
What is new?
Hirschsprung’s disease (HD) is a congenital absence of enteric ganglion cells in the distal bowel, causing obstruction and proximal dilation. While usually detected in the neonatal period, delayed presentation is common in resource-limited settings due to poor awareness and limited diagnostics. Traditional staged surgery with colostomy increases complications and caregiver burden. The transanal endorectal pull-through (TAPT) offers a single-stage, minimally invasive option that avoids colostomy and laparotomy, though concerns remain in low-resource environments lacking frozen section, imaging, and pediatric anesthesia support. This manuscript presents eight children with rectosigmoid HD managed with single-stage TAPT, demonstrating reliable transition-zone identification without frozen section and good early functional outcomes. The findings show that TAPT is safe, feasible, and effective even in constrained settings.
Acknowledgments
We would like to express our sincere appreciation to the pediatric surgery team at Muhimbili National Hospital for their unwavering support throughout the management of these cases. We are especially grateful to the visiting pediatric surgeons and pediatric anesthesiologists whose expertise, guidance, and collaborative decision-making significantly strengthened both the perioperative and postoperative care of our patients.
Our gratitude also extends to the nursing staff, anesthetic officers, radiology department, and pathology team, whose dedication and teamwork were essential in ensuring timely diagnosis, smooth operative workflow, and high-quality perioperative care despite the limitations of our setting. We acknowledge the invaluable cooperation of the patients and their families, whose trust and commitment made this work possible.
List of Abbreviations
| HAEC | Hirschsprung-associated enterocolitis |
| HD | Hirschsprung’s disease |
| IV | Intravenous |
| TAPT | Transanal endorectal pull-through |
Ethical Approval
Ethical approval for this study was granted by the institutional Review Ethical Committee. All procedures performed were in accordance with institutional and national research ethics standards.
Patient consent
Written informed consent was obtained from the parents/legal guardians of all pediatric patients included in this case series. Copies of the consent forms are available for review by the Editor-in-Chief of this journal on request.
Funding
None.
Conflict of interest
The authors declare that they have no conflict of interest regarding the publication of this article.
Author details
Mathayo Shadrack1,2,3, Alex Mashaka1,4,5, Mohammed Sultan Salim1,2,4, Ally Hamisi Mwanga1,2,4, Zaitun Bokhary1,2,4
- Muhimbili University of Health and Allied Sciences (MUHAS), Dar es Salaam, Tanzania
- Department of Surgery (Pediatric Surgery Unit), Muhimbili University of Health and Allied Sciences (MUHAS), Dar es Salaam, Tanzania
- Department of Pediatric Surgery, Kilimanjaro Christian Medical Centre (KCMC), Moshi, Tanzania
- Muhimbili National Hospital (MNH), Dar es Salaam, Tanzania
- Department of Pathology, Muhimbili National Hospital (MNH), Dar es Salaam, Tanzania
Summary of the case
This case series reports 8 children aged 2.5-9 years with rectosigmoid Hirschsprung’s disease (HD) who underwent single-stage transanal endorectal pull-through (TAPT) at a tertiary referral hospital in Tanzania. All patients presented with long-standing constipation and abdominal distension, and diagnosis was confirmed by contrast enema and full-thickness rectal biopsy. Preoperative optimization included rectal irrigations, nutritional rehabilitation, intravenous antibiotics, and correction of fluid and electrolyte imbalances. TAPT was performed without intraoperative frozen section, with intraoperative assessment of bowel caliber and vascularity guiding the resection margin. Median length of resected bowel was 20 cm, and time to first stool ranged from 24 to 48 hours. One patient (12.5%) developed mild Hirschsprung-associated enterocolitis (HAEC), which resolved with conservative management. No anastomotic leaks, strictures, or fecal incontinence occurred. At a median follow-up of 4 months, all patients had 1-2 soft stools daily, achieved age-appropriate continence, and demonstrated improved weight gain and nutritional status. This series demonstrates that single-stage TAPT is safe, effective, and feasible in resource-limited settings even in the absence of frozen section support.
References
- Amiel J, Lyonnet S. Hirschsprung disease, associated syndromes, and genetics: a review. J Med Genet. 2001;38(11):729–39. https://doi.org/10.1136/jmg.38.11.729
- Kenny SE, Tam PK, Garcia-Barceló M. Hirschsprung’s disease. Semin Pediatr Surg. 2010;19(3):194–200. https://doi.org/10.1053/j.sempedsurg.2010.03.004
- Ameh EA, Bickler SW, Lakhoo K. Pediatric Surgery in Africa. Berlin, Germany: Springer; 2011.
- Georgeson KE, Fuenfer MM, Hardin WD Jr. Primary pull-through for Hirschsprung’s disease in the newborn. J Pediatr Surg. 1999;34(1):148–51.
- De La Torre-mondragón L, Ortega-Salgado JA. Transanal endorectal pull-through for Hirschsprung’s disease. J Pediatr Surg. 1998;33(8):1283–6. https://doi.org/10.1016/S0022-3468(98)90169-5
- Langer JC. Transanal pull-through for Hirschsprung disease: technique, indications, and outcomes. J Pediatr Surg. 2013;48(8):1816–21.
- Minneci PC, Deans KJ, Kim P, Eaton S, Campbell BT, Jaksic T. Long-term outcomes of transanal endorectal pull-through for Hirschsprung disease. Ann Surg. 2013;258(3):473–80
- Osifo OD, Evbuomwan I. Outcome of transanal endorectal pull-through in a Nigerian tertiary center. Afr J Paediatr Surg. 2011;8(1):50–5.
- Rintala RJ, Pakarinen MP. Long-term outcomes of Hirschsprung’s disease. Semin Pediatr Surg. 2012;21(4):336–43. https://doi.org/10.1053/j.sempedsurg.2012.07.008
- Holschneider AM, Puri P, Homsy YL, Langer JC, Teitelbaum DH, Georgeson KE, et al. Hirschsprung’s disease and allied disorders–clinical management. Pediatr Surg Int. 2007;23(2):97–107.
- Teitelbaum DH, Qualman SJ, Caniano DA. Transition zone pathology in Hirschsprung disease. J Pediatr Surg. 2005;40(1):85–92.
- Pastor AC, Osman F, Teitelbaum DH, Langer JC, Brandt ML, Holschneider AM, et al. Development of Hirschsprung-associated enterocolitis. J Pediatr Surg. 2009;44(1):206–12.
- Lal P, Agarwal PN, Malik VK, Khurana N, Puri P. Transanal pull-through for Hirschsprung disease in older children. Pediatr Surg Int. 2007;23:119–23.
- Moore SW, Zaahl M, Numanoglu A, Rode H. Hirschsprung disease in Africa. Pediatr Surg Int. 2008;24(10):1027–30.
- Nasr A, Langer JC. Transanal pull-through for Hirschsprung disease: systematic review and meta-analysis. J Pediatr Surg. 2014;49(1):142–8.
- Agha RA, Mathew G, Rashid R, Franchi T, Rosin D, Albrecht J, et al. The PROCESS 2025 guideline: updated reporting standards for case series in surgery. Premier J Sci. 2025;10:100080.
Keywords: Hirschsprung’s disease, transanal endorectal pull-through, rectosigmoid aganglionosis, pediatric surgery, resourcelimited settings.


Publication History
Received: November 29, 2025
Revised: January 02, 2026
Accepted: February 27, 2026
Published: April 13, 2026
Authors
Mathayo Shadrack
Muhimbili University of Health and Allied Sciences (MUHAS), Dar es Salaam, Tanzania.
 ORCID
Alex Mashaka
Muhimbili University of Health and Allied Sciences (MUHAS), Dar es Salaam, Tanzania.
Mohammed Sultan Salim
Muhimbili University of Health and Allied Sciences (MUHAS), Dar es Salaam, Tanzania.
Ally Hamisi Mwanga
Muhimbili University of Health and Allied Sciences (MUHAS), Dar es Salaam, Tanzania.
Zaitun Bokhary
Muhimbili University of Health and Allied Sciences (MUHAS), Dar es Salaam, Tanzania.