European Journal of Medical Case Reports
Volume 10(5):149–153
Bilateral periorbital post-emetic purpura - a case report
Muhammad Nasir1* , Johnny Canlas¹
Correspondence to: Muhammad Nasir
*Paediatric Department, Queens Hospital Romford, Romford, United Kingdom.
Email: dr_m.nasir@hotmail.com
Full list of author information is available at the end of the article.
Received: 16 November 2025 | Revised (1): 02 January 2026 | Accepted: 04 February 2026
ABSTRACT
Background:
Post-emetic purpura is a benign condition characterized by the presence of non-blanchable petechiae or purpura (typically in the distribution of the superior vena cava), usually resulting from a sudden increase in intrathoracic pressure after episodes of vigorous vomiting. Despite its often alarming clinical appearance, which can simulate serious hematologic or infectious diseases, it is a self-limiting occurrence with no systemic implications.
Case Presentation:
We report the case of a 4-year-old female patient who presented with periorbital purpura after an episode of intense vomiting. Physical examination revealed an erythematous, non-bleachable and bilateral rash that was restricted to the region around the eyes, with no other relevant clinical changes. The condition evolved with spontaneous resolution, without the need for therapeutic interventions.
Conclusion:
Recognition of post-emetic purpura is essential to avoid additional investigations and reduce anxiety of family members, contributing to a safer and more efficient clinical approach.
Keywords:
Petechiae, paediatric, benign purpura, skin diseases, periorbital purpura.
Introduction
Purpura and petechiae are non-blanchable lesions caused by blood leaking into the skin [1,2]. While purpura can indicate a wide range of underlying conditions, post-emetic purpura is a specific type that occurs after severe vomiting or other activities that increase intrathoracic pressure [2,3]. Post-emetic purpura typically presents as petechiae or non-blanchable purpura on the face, especially around the eyes [4]. It is important to differentiate post-emetic purpura from more serious conditions (such as meningococcemia, trauma, thrombocytopenia, or coagulopathies), although its appearance can be alarming, post-emetic purpura is not associated with hematologic or systemic abnormalities [5,6]. Although its appearance may generate concern in caregivers and health professionals, the clinical picture is typically harmless and resolves spontaneously. This case report aims to raise awareness of post-emetic purpura among health professionals and to provide guidance on its diagnosis and treatment, highlighting the importance of recognizing this benign condition to avoid unnecessary investigations and interventions.
Case Presentation
A 4-year-old girl presented with an unusual rash around both eyes. She was well until the previous day, when she developed 4-5 episodes of loose stools without blood or mucus. On the evening of presentation, she had one episode of forceful, non-bilious, non-projectile vomiting.
The clinical evolution of the case is presented schematically in a timeline, highlighting the initial state of well-being, the appearance of diarrhoea episodes the day before presentation, the occurrence of vomiting associated with the appearance of a periorbital rash on the day of admission, and the complete resolution of skin lesions 2 days after discharge, facilitating the understanding of the temporal sequence of clinical events (Figure 1).
The rash was described as bright red around both eyes, affecting the upper and lower eyelids (Figure 2A and B). It was non-blanching and not painful on palpation. There was no swelling or spreading of the rash. The eyes were otherwise normal, with no redness or pain. There was no fever or rash elsewhere on the body. The patient was tolerating oral intake well, had no urinary complaints, headache, or visual complaints. She was eating and drinking well, with no further episodes of vomiting.
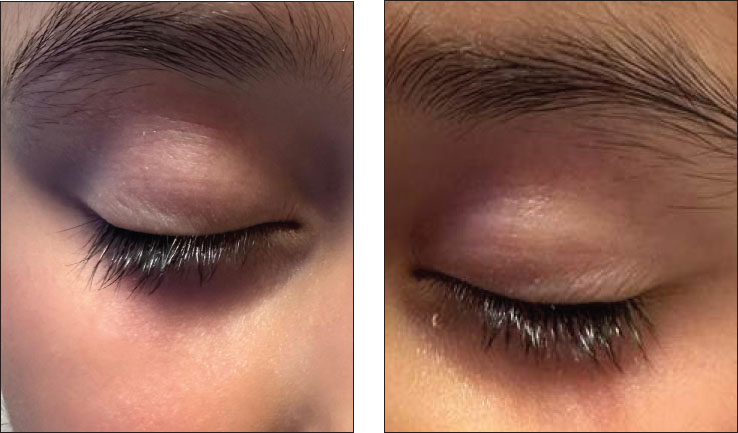
Figure 1. Timeline of a 4-year-old girl presenting an unusual rash around both eyes.
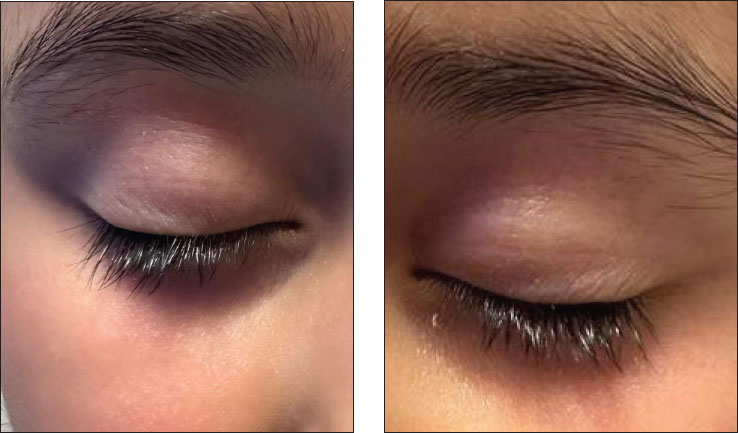
Figure 2. Purpuric lesions bilateral periorbital area after vomiting. (A) Right lateral view showing purpuric lesions; (B): Left lateral view showing purpuric lesions.
Past medical history
The patient had a history of eczema, with dryness on both eyelids prior to the rash. There was no recent travel history, and she was immunized up to date. She had no known allergies.
Physical examination (O/E)
- General: Active, alert, smiling, and playful.
- Cardiovascular: Pink, well-perfused, capillary refill time less than 2 seconds.
- Respiratory: No respiratory distress, bilateral equal air entry without any added sounds.
- Cardiovascular: Normal heart sounds.
- Abdomen: Soft and non-tender abdomen, no visceromegaly.
- Neurology: Active, alert, Glasgow Coma Scale 15/15. No focal neurological deficit, no neck stiffness.
- ENT: Bilateral large tonsils, not painful or congested.
Investigations
- Neutrophils: 8.4 × 10^9/l
- White blood cell count: 11.3 × 10^9/l
- C-reactive protein: 10 mg/l
- Blood Gas: pH: 7.31, Base Excess: −6.1
Management
The patient was admitted for consultant review. She was discharged home with topical steroids. The rash resolved completely within 2 days (Figure 3).
Discussion
Postemetic purpura is a rare and benign self-limiting clinical manifestation characterized by the appearance of petechiae, usually on the face, after episodes of sudden increase in intrathoracic pressure, such as with vigorous vomiting, intense coughing, physical exertion or Valsalva maneuvers [1-3,7]. This phenomenon is secondary to the rupture of superficial dermal capillaries, resulting in extravasation of blood into the subcutaneous tissues, especially in areas with fine and delicate vascularization.
The differential diagnosis of facial purpura in children includes potentially serious conditions, such as meningococcemia, Henoch-Schönlein purpura, and acute hemorrhagic edema of infancy [8]. However, the absence of fever, systemic signs, and other specific clinical manifestations contributed to the exclusion of these etiologies. This case illustrates a classic presentation of post-emetic purpura in a young child. The sudden onset of a non-blanching rash around the eyes following an episode of forceful vomiting is highly suggestive of this diagnosis [1,3,7]. The increased intrathoracic pressure during vomiting leads to rupture of small blood vessels in the periorbital area, resulting in the characteristic petechiae or purpura [3,9]. It’s important to note that while the appearance of the rash can be alarming to parents and clinicians, post-emetic purpura is a benign and self-limiting condition [1].
The laboratory findings, mild leukocytosis and mild elevation of C-reactive protein, were compatible with a mild inflammatory process, probably related to the transient gastrointestinal condition. Clinically, she remained in good general condition, with no relevant changes on physical examination. The skin lesions, restricted to the periorbital region, were painless, nonpruritic, and without progression, typical characteristics of postemetic purpura. The diagnosis, of an essentially clinical nature, was supported by the benign evolution and the exclusion of other more serious causes of petechiae, such as idiopathic thrombocytopenic purpura, vasculitis, coagulopathies and mistreatment. In this case, the elevated neutrophils and CRP levels were likely related to the preceding diarrheal illness. The blood gas results indicate a mild metabolic acidosis, which could also be attributed to the diarrhoea.
In this context, a careful assessment for clinical red flags was essential to support the diagnostic reasoning. The absence of fever, systemic toxicity, rapid clinical deterioration, or spreading of the rash strongly argued against invasive bacterial infection. Hematological disorders, including thrombocytopenia related conditions, were excluded based on the normal platelet count and the absence of mucosal bleeding, generalized bruising, lymphadenopathy, or hepatosplenomegaly. Additionally, there were no clinical features suggestive of vasculitis or coagulopathy, and the history and injury distribution were not consistent with traumatic or non-accidental causes. Taken together, the lack of these warning signs, along with the strict periorbital localization following forceful vomiting and the rapid spontaneous resolution, reinforced the diagnosis of post-emetic purpura.
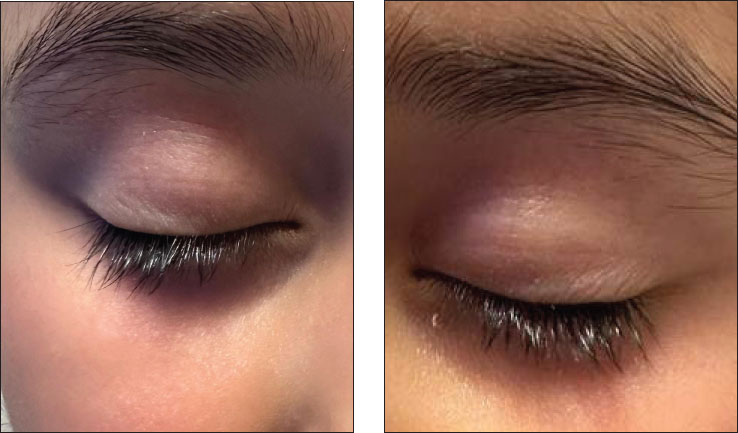
Figure 3. Complete resolution of periorbital postemetic purpura 2 days after the vomiting episode, without the need for systemic interventions. Lesions did not leave pigmentary or scarring sequelae. (A) Right lateral view; (B): Left lateral view.
From an epidemiological perspective, this type of presentation is more commonly reported in adults but can occur at any age. It is likely underreported in the paediatric population. Clinical familiarity with this condition is essential to avoid unnecessary interventions, such as invasive hematological investigations or inappropriate antibiotic use. This case adds to the medical literature by underscoring the importance of recognizing post-emetic purpura in young children and the role of careful clinical assessment. The benign clinical progression and rapid resolution without complications further reinforce its non-alarming nature.
Conclusion
In conclusion, post-emetic purpura is a harmless and temporary condition that usually appears as small red spots around the eyes, usually after episodes of vomiting or intense effort, such as loud crying or coughing. Although its appearance may frighten parents, it is common and not serious. Therefore, a careful conversation with the family and a thorough physical examination are essential to recognize the condition and avoid unnecessary tests or treatments. When health professionals are familiar with this condition, they can offer the right guidance and reassure those responsible. The fact that the spots are located only on the face and are not accompanied by other symptoms helps to confirm that it is something benign. Including post-emetic purpura in the diagnostic possibilities allows for safer, faster and more compassionate care.
What’s new?
This manuscript presents a case involving a 4-year-old girl who developed isolated, bilateral periorbital purpura immediately after intense vomiting, with no additional clinical abnormalities. The case highlights the characteristic presentation and benign course of post-emetic purpura in young children and reinforces the importance of recognizing this entity to prevent unnecessary diagnostic workup and alleviate caregiver anxiety.
List of Abbreviations
| CRP | C-reactive protein |
| ENT | Ear, nose, and throat |
| O/E | On Examination |
| pH | potential of hydrogen |
Authors contributors
MN and JC drafted the initial manuscript, performed the relevant literature search, critical review and revision of the manuscript. All the authors approve the manuscript as submitted and agree to be accountable for all the aspects of the work.
Conflict of interests
The authors declare that there is no conflict of interest regarding the publication of this article.
Informed Consent
Written informed consent was obtained from the parents.
Ethical Approval
Ethical approval is not required at our institution for anonymous case reports.
Funding
The authors have not declared a specific grant for this research from any funding agency in the public, commercial or not-for-profit sectors.
Author details:
Muhammad Nasir¹, Johnny Canlas¹
- Paediatric Department, Queen’s Hospital Romford, Romford, United Kingdom
References
- Ibraheim MK, Gavvala S. Problematic Purpura. Cureus. 2021;13(2):e13473. https://doi.org/10.7759/cureus.13473
- Galadari AA, Otaibi MA. Valsalva purpura on the face of a 7-year-old child. J Med Life. 2023;16(12):1869–71. https://doi.org/10.25122/jml-2023-0447
- Meghwal B, Balai M. Post-vomiting purpura. Nasza Dermatol Online. 2017;8(4):505–6. https://doi.org/10.7241/ourd.20174.146
- Bhanja DB, Mondal S, Sil A, Das A, Panigrahi A, Biswas SK. Post-emesis periorbital purpura in hyperemesis gravidarum. Int J Dermatol. 2021;60(3):e117–9. https://doi.org/10.1111/ijd.15292
- Thomas AE, Baird SF, Anderson J. Purpuric and petechial rashes in adults and children: initial assessment. BMJ. 2016;352:1285. https://doi.org/10.1136/bmj.i1285
- Mizerik M, Yao L, Sudheendra M, El Atrache R, Davila-Williams D, Risen S. Congenital thrombotic thrombocytopenic purpura presenting as extensive multifocal ischemic strokes with aphasia and hemiplegia in a 3-year-old male patient (P8-14.012). Neurology. 2025;104(7_Supplement_1):3907. https://doi.org/10.1212/WNL.0000000000211317
- Burke M, Marks J. Purpura associated with vomiting in pregnancy. BMJ. 1973;2(5864):488. https://doi.org/10.1136/bmj.2.5864.488-c
- Neves C, Brito N, Santos D, Mota L. Purpuric lesions: what diagnosis?. Case Rep. 2016;2016:bcr2015210154. https://doi.org/10.1136/bcr-2015-210154
- Kaliyadan F, Kuruvilla JP. Post-vomiting purpura. Indian Dermatol Online J. 2016;7(5):456–7. https://doi.org/10.4103/2229-5178.190510
Summary of the case
| 1 | Patient (gender, age) | Female, 4-years-old |
| 2 | Final diagnosis | Post-emetic purpura |
| 3 | Symptoms | Loose stools without blood or mucus; one episode of forceful, non-bilious, non-projectile vomiting and rash around both eyes |
| 4 | Medications | Topical steroids |
| 5 | Clinical procedure | No |
| 6 | Specialty | Paediatrics |
Keywords: Petechiae, paediatric, benign purpura, skin diseases, periorbital purpura.


Publication History
Received: November 16, 2025
Revised: January 02, 2026
Accepted: February 04, 2026
Published: April 13, 2026
Authors
 ORCID
Johnny Canlas
Paediatric Department, Queen’s Hospital Romford, Romford, United Kingdom.