European Journal of Medical Case Reports
Volume 10(5):164–171
Post-abortum Anti-N-Methyl-D-aspartate encephalitis mimicking bacterial encephalitis: a case report and literature review
Tue Bui Chau1, An Nguyen Thanh1*, Loc Le Quang2 , Thang Huynh Xuan2, Lap Dinh Van1
Correspondence to: An Nguyen Thanh
*Neurology Department, Cho Ray Hospital, Ho Chi Minh City, Vietnam.
Email: drthanhan96@gmail.com
Full list of author information is available at the end of the article.
Received: 08 December 2025 | Revised (1): 10 February 2026 | Accepted: 28 February 2026
ABSTRACT
Anti-NMDA receptor encephalitis is a severe autoimmune encephalitis characterized by progressive neuropsychiatric symptoms and the presence of Immunoglobulin G antibodies against the GluN1 subunit of NMDA receptors. We report a case of a previously healthy 20-year-old woman who developed memory impairment, seizures, and progressive decline in consciousness shortly after first-trimester pregnancy termination. Initial cerebrospinal fluid (CSF) findings showed marked neutrophilic pleocytosis, mimicking bacterial meningitis, leading to delayed diagnosis. Anti-NMDAR antibodies were subsequently detected in the CSF, confirming the diagnosis. The patient required intensive care management, including mechanical ventilation and treatment of refractory status epilepticus. First-line therapy with high-dose corticosteroids and intravenous immunoglobulin resulted in partial improvement, followed by significant recovery after rituximab administration. This case highlights diagnostic challenges related to atypical CSF patterns and suggests that pregnancy termination may represent a temporal association with disease progression in susceptible individuals. Clinicians should consider autoimmune encephalitis in acute neuropsychiatric presentations following abortion.
Keywords:
Anti-NMDAR encephalitis, autoimmune encephalitis, post-abortum complications, immunotherapy, case report.
Introduction
Anti-NMDAR encephalitis is an autoimmune condition marked by diverse neuropsychiatric symptoms and Immunoglobulin G (IgG) antibodies directed against the NR1 subunit of NMDA receptors within the central nervous system (CNS) [1]. Although the annual incidence is low (approximately 1 per 1.5 million population), it is the most well-known and likely the most prevalent autoimmune encephalitis.
This autoimmune encephalitis arises from the deposition and adhesion of IgG1 and IgG3 to the NMDA receptor (NR1) subunit. While some cases are triggered by ovarian teratomas, most occur without an identifiable cause. Intrathecal B-cell activation remains central to disease pathogenesis [2].
Anti-NMDA receptor encephalitis is characterized by a distinct progression of clinical phases: prodrome, psychiatric phase, neurologic complications, recovery, and late phase (Figure 1) [3]. Approximately 70% of patients experience a viral-like prodrome approximately 5 days before the onset of psychiatric symptoms such as psychosis, including delusions, perceptual disturbances, disorganized thoughts, anxiety, agitation, mood swings, and personality changes. Neurologic complications include seizures, catatonia, dyskinesias, autonomic instability, and hypoventilation. Recovery occurs in reverse order of symptom onset, and although 85% eventually regain near-normal function, many have lingering executive or behavioral deficits. The relapse rate is approximately 20% to 25%.
Case Report
A previously healthy 20-year-old female was admitted to the hospital due to recurrent seizures accompanied by progressive alterations in consciousness. Approximately 19 days before admission, she experienced short-term memory impairment as the first symptom without any behavioral disturbances. On the third day of her illness, she noticed delayed menstruation and subsequently discovered an unplanned six-week pregnancy. Medical termination was performed, which was complicated by retained products of conception. Following the procedure, her cognitive symptoms continued to worsen.
On the 16th day of her illness, she experienced her first generalized tonic-clonic seizure. She was subsequently admitted to a provincial hospital, where initial brain MRI findings were unremarkable. The first CSF analysis revealed marked pleocytosis of 553 cells/mm³ with 90% neutrophils, elevated protein of 0.52 g/l, and a CSF-to-serum glucose ratio of 3.4/3 mmol/l. A subsequent lumbar puncture confirmed persistent pleocytosis of 402 cells/mm³ (70% neutrophils), protein 0.64 g/l, and a CSF-to-serum glucose ratio of 3.5/6 mmol/l. Based on these findings, bacterial meningitis was suspected, and she received vancomycin and ceftriaxone. However, her condition progressively deteriorated with recurrent seizures and declining consciousness, prompting referral to Cho Ray Hospital on the 19th day.
Figure 1. Phases of illness in anti-NMDA receptor encephalitis [3].
Figure 2. Brain MRI shows hyperintense of bilateral temporal lobe on FLAIR.
Figure 3. Timeline of clinical course, diagnosis, and treatment.
Table 1. Literature review of post-abortum anti-NMDA receptor encephalitis.
| STUDY | AGE | ONSET | SYMPTOMS | CSF FINDINGS | TREATMENT | IMMUNOTHERAPY ESCALATION | ICU REQUIREMENT | OUTCOME |
|---|---|---|---|---|---|---|---|---|
| Rozaleen Aleyadeh et al [7] | 20 and 27 | 2 weeks after abortion | Psychosis, catatonia, dysautonomia | Not reported | IVIG | No | No | Full recovery |
| Saied Zakaria et al [8] | 32 | 1 week after 1st trimester abortion | Psychomotor agitation, memory disorders, fever, confused, generalized seizure | Lymphocytic pleocytosis | IV corticosteroid 1g x 5 days then tapered oral prednisone | No | No | Partial recovery with residue memory disturbance and psychiatric symptoms |
| Present case | 20 | 1 day after 1st trimester abortion | Memory disorders, fever, confused, status epilepticus, coma | Initial: neutrophilic pleocytosis (90%); Later: lymphocytic (80%) | IV corticosteroid 1g x 5 days then tapered oral prednisone, IVIG, Rituximab | Yes | Yes (mechanical ventilation 15 days) | Partial recovery with residue memory disturbance |
Upon transfer, the patient was drowsy, with a Glasgow Coma Scale (GCS) score of E4V1M4 = 9, afebrile, mild neck stiffness, and frequent brief seizures. Given the atypical clinical course and lack of response to antibiotics, viral and autoimmune encephalitis were considered. Laboratory evaluation included autoimmune screening tests such as ANA, anti-dsDNA, complement levels (C3, C4), and procalcitonin, all of which were within normal limits. A third lumbar puncture was performed, and CSF was tested for HSV PCR and anti-NMDA receptor antibodies. Broad-spectrum antibiotics (meropenem, vancomycin) and acyclovir were initiated.
The third CSF analysis on day 20 revealed a significant reduction in cell count to 54 cells/mm³, with 80% lymphocytes, protein 58.8 mg/dl, normal glucose, and negative HSV PCR. This effectively eliminated bacterial and viral meningitis and strongly suggested autoimmune encephalitis. On day 21, the patient experienced multiple generalized seizures that were refractory to phenytoin, valproate, and levetiracetam. Consequently, endotracheal intubation, invasive mechanical ventilation, and continuous intravenous sedation with midazolam at 0.03 mg/kg/h were initiated. Electroencephalography (EEG) demonstrated generalized slowing without epileptiform discharges or extreme delta brush.
On the 22nd day, anti-NMDAR antibodies were detected in the CSF, confirming the diagnosis of anti-NMDA receptor encephalitis. Consequently, acyclovir and antibiotics were discontinued. The neurology team was consulted, and on the 23rd day, the patient was initiated on high-dose intravenous methylprednisolone (1 g/day for 5 days) in combination with intravenous immunoglobulin (0.4 g/kg/day for 5 days). Multiple antiepileptic drugs were also continued, including midazolam IV, valproate, levetiracetam, phenytoin, and topiramate. Imaging studies ruled out ovarian teratoma.
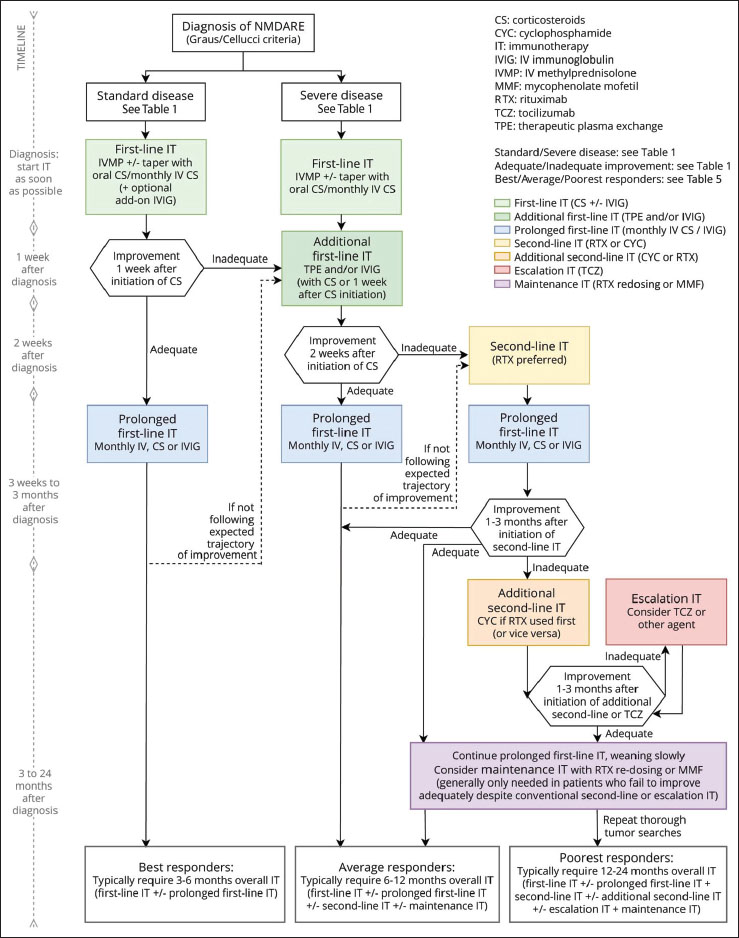
Figure 4. International consensus recommendations for the treatment of first event of pediatric NMDAR antibody encephalitis (NMDARE) [5].
Despite the aggressive therapy, recurrent seizures persisted, prompting the initiation of propofol infusion at 2 mg/kg/h to achieve deeper sedation. Follow-up EEG demonstrated persistent diffuse slowing but no clinical or electrographic seizures. Repeat brain MRI revealed bilateral temporal lobe hyperintensities on FLAIR sequences without contrast enhancement, diffusion restriction, or mass effect. Later brain MRI revealed bilateral temporal lobe hyperintensities on FLAIR sequences (Figure 2). The absence of gadolinium enhancement and the symmetric distribution suggested seizure-related changes (postictal edema) rather than primary inflammatory or infectious lesions. Additionally, the initial MRI on day 16 had been completely normal, making acute inflammatory encephalitis less likely. The temporal evolution of MRI findings correlated with seizure activity rather than progressive inflammation.
The patient improved after five days of combined steroids and IVIG. Seizures resolved, propofol was discontinued, and midazolam was tapered. However, she developed ventilator-associated pneumonia on day 30, with sputum cultures growing multidrug-resistant Pseudomonas aeruginosa, treated successfully with high-dose meropenem and vancomycin.
Due to insufficient neurological improvement, rituximab (1,000 mg) was administered on day 35. Her condition improved rapidly thereafter, enabling successful extubation and transition to oral steroids. A second rituximab dose was planned two weeks later. She was subsequently transferred for continued rehabilitation. Long-term follow-up with repeat ovarian imaging at 6 and 12 months is planned. The clinical course, diagnostic process, and treatment timeline are summarized in Figure 3.
Discussion
The diagnosis of anti-NMDA receptor autoimmune encephalitis is based on the criteria proposed by Graus et al., [4] requiring a rapid onset of four out of six core symptom groups in addition to supportive CSF or EEG abnormalities, following reasonable exclusion of other etiologies. In our patient, the diagnosis of probable autoimmune encephalitis could have been reasonably suspected as early as day 16 when she presented with: Rapidly progressive working memory deficits (day 1 onset), new-onset seizures (day 16), CSF pleocytosis (553 cells/mm³), and altered mental status with declining consciousness. Although the neutrophil-predominant CSF initially suggested bacterial meningitis, the combination of subacute cognitive decline preceding seizures, lack of fever, and negative bacterial cultures should have raised suspicion for autoimmune etiology. The third CSF analysis on day 20, which demonstrated lymphocytic predominance (80% lymphocytes) and negative HSV PCR, further supported this diagnosis even before antibody confirmation on day 22. This case underscores the importance of maintaining a high index of suspicion for autoimmune encephalitis in patients with acute neuropsychiatric presentations and CSF pleocytosis, even when initial findings mimic infectious etiologies. Early recognition and empiric immunotherapy initiation may improve outcomes, particularly in severe cases.
The marked neutrophilic pleocytosis observed in our patient represents an important diagnostic pitfall. While CSF lymphocytic pleocytosis is typical in anti-NMDAR encephalitis, neutrophil-predominant CSF has been documented in early disease phases. A systematic review by Gresa-Arribas et al. reported that approximately 10% to 15% of anti-NMDAR encephalitis cases present with initial neutrophilic pleocytosis, which may lead to misdiagnosis as bacterial meningitis. The evolution from neutrophilic to lymphocytic predominance, as observed in our patient (90% neutrophils on day 16% to 80% lymphocytes on day 20), represents a recognized temporal pattern in autoimmune encephalitis and has been reported in other cases. This CSF evolution, combined with negative bacterial cultures, lack of response to antibiotics, and progressive neuropsychiatric deterioration, prompted reconsideration of the diagnosis. Clinicians should be aware that neutrophilic CSF does not exclude autoimmune encephalitis, particularly in the first 1 to 2 weeks of symptom onset. Repeat lumbar puncture demonstrating lymphocytic shift, along with negative infectious workup, should trigger early autoimmune antibody testing and consideration of empiric immunotherapy in severe cases.
Diagnostic challenges persist because early symptoms and laboratory findings may be nonspecific. Up to half of patients previously labeled with lethargic dyskinetic encephalitis later tested positive for anti-NMDAR antibodies. Moreover, 20% to 30% of patients with herpes simplex virus (HSV) encephalitis develop anti-NMDAR antibodies during relapse, despite no evidence of HSV reactivation [2].
Although universal guidelines are lacking, the International Consensus Recommendations for pediatric NMDAR encephalitis provide a commonly adopted framework (Figure 4) [5]. Early immunotherapy improves outcomes and reduces long-term disability. First-line therapy includes pulse corticosteroids, often combined with IVIG or plasma exchange, particularly in severe cases involving altered consciousness, refractory seizures, autonomic instability, or respiratory compromise. Patients who fail to improve within 2-4 weeks should receive second-line therapy, with rituximab preferred over cyclophosphamide. In severe cases requiring intensive care measures, early rituximab initiation may be beneficial. Screening for and removing underlying tumors, especially ovarian teratomas, significantly improves outcomes.
Supportive care remains essential. Seizure management often involves multiple antiepileptic drugs, and refractory cases may need continuous anesthetic infusions. Vigilance for complications—such as nosocomial infections, pressure ulcers, and thrombosis—is mandatory. Long-term follow-up is necessary to monitor cognitive recovery and detect relapses.
Returning to our case, we encountered a patient presenting with a clinical picture highly suggestive of autoimmune encephalitis. However, the diagnosis proved challenging due to misleading CSF findings, which exhibited neutrophil-predominant pleocytosis, mimicking bacterial meningitis, in conjunction with a normal initial brain MRI. Ultimately, CSF antibody testing confirmed anti-NMDAR encephalitis, underscoring the necessity of antibody analysis even when early findings mimic infectious etiologies.
Upon confirmation of the diagnosis, which was on the 22th day of the illness, our patient was marked as “severe disease” due to status epilepticus, coma, and mechanical ventilation. We promptly initiated first-line immunotherapy comprising high-dose corticosteroids and IVIG. According to the International Consensus Recommendations for pediatric NMDAR encephalitis, second-line immunotherapy is generally considered in patients who demonstrate an inadequate response after two weeks of first-line treatment. Therefore, in our case, after high-dose corticosteroids and IVIG, we decided to observe for approximately two weeks to assess therapeutic response. Despite partial improvement in consciousness, she remained ventilator-dependent; therefore, rituximab was used on day 35 (two weeks after first-line therapy) based on the consensus stepwise escalation strategy. Besides, the administration of rituximab was as part of an strategy to optimize long-term outcomes.
Although a case report [6] suggests that early use of second-line therapy (which was ten days after first-line therapy) may be beneficial in severe ICU cases, this approach remains supported by limited high-quality evidence. In addition, early administration of rituximab has a risk of excessive immunosuppression, which may increase the likelihood of infections and infection-related mortality. In our patient, she was on mechanical ventilation and had a high risk for infections; therefore, we decided to delay rituximab until inadequate response to first-line therapy after two weeks, as the consensus instructs. This decision gave a balance between controlling autoimmune neuroinflammation and minimizing the risk of infectious complications.
Our case shares notable similarities with those documented by Rozaleen Aleyadeh et al [7] and Saied Zakaria et al [8], both of which described anti-NMDAR encephalitis developing following pregnancy termination. A comparison between our case with previously reported cases is summarized in Table 1. These observations suggest suggest that pregnancy termination may potentially act as an immunological trigger for autoimmune encephalitis in susceptible individuals. In our patient, memory disturbances began prior to the abortion but markedly worsened after the procedure. This trajectory differs from the expected course of pregnancy-related dysautonomia, which normally improves once the pregnancy is terminated. Accordingly, this case could be more appropriately classified as post-abortum encephalitis. However, critical differences exist: in the previously reported cases, patients did not progress to deep coma and demonstrated rapid clinical improvement with high-dose corticosteroid monotherapy alone. The temporal sequence suggests that pregnancy termination may have acted as a contributing factor to disease progression rather than the primary trigger. While abortion temporally preceded clinical deterioration, we emphasize that this represents a temporal association rather than a proven causal relationship. The exact immunological mechanisms linking pregnancy termination to autoimmune encephalitis remain speculative. Larger studies are required to confirm whether abortion could serve as a potential trigger or play a role in the worsening pathogenesis of this condition.
Comparative analysis of reported post-abortum anti-NMDAR encephalitis cases reveals important clinical distinctions. While all three cases share the temporal association with pregnancy termination, our patient demonstrated significantly greater disease severity. A critical distinguishing feature of our case is the initial neutrophilic CSF pleocytosis (90% neutrophils), which mimicked bacterial meningitis and delayed diagnosis—a finding not reported in previous post-abortum cases. The evolution to lymphocytic predominance on repeat lumbar puncture was key to diagnostic reconsideration. Furthermore, our patient required treatment escalation to second-line immunotherapy with rituximab, whereas previously reported cases responded to first-line therapy alone (corticosteroids or IVIG monotherapy). These differences suggest clinical heterogeneity in post-abortum anti-NMDAR encephalitis, with some patients experiencing mild, self-limited disease and others developing life-threatening complications requiring intensive care and aggressive immunosuppression. The severity in our case may reflect delayed diagnosis due to atypical CSF findings, underlying individual immunological factors, or the specific circumstances of pregnancy termination (retained products of conception). This heterogeneity underscores the importance of early recognition, prompt antibody testing, and readiness to escalate therapy in severe presentations.
Anti-NMDA receptor encephalitis relation with pregnancy has garnered attention from physicians worldwide. Tadashi Doden et al [9] examined six cases of anti-NMDAR encephalitis with symptom onset ranging from 1 week to 3 months after vaginal delivery. Most patients presented with psychiatric symptoms; seizures occurred in four cases. Ovarian teratomas were identified in half of the patients. All responded to standard immunotherapy. Several pathophysiological mechanisms have been proposed to explain disease development in the postpartum setting. The dramatic surge in estrogen levels during pregnancy may accelerate B-cell maturation, enhance interleukin-10 secretion, and promote the formation of autoreactive lymphocytes, ultimately leading to the production of anti-NMDA receptor autoantibodies. Childbirth or abortion may lead to symptom resolution in some patients with anti-NMDAR encephalitis [10], which contrasts with post-abortum encephalitis, where symptoms typically arise or worsen following fetal delivery. Additional contributing factors may include alterations in immune tolerance and potential retrograde ovarian infections that trigger the postpartum onset of the condition. Disease relapse following initial resolution is relatively common, with approximately 15% to 25% of patients experiencing recurrence, typically within the first 2 years after initial presentation [11].
Conclusion
In conclusion, anti-NMDA receptor encephalitis remains underdiagnosed due to the variability of the initial symptoms and nonspecific initial investigations. Anti-NMDA receptor encephalitis should be considered in patients presenting with acute neuropsychiatric symptoms and CSF pleocytosis, even when neutrophil predominance initially suggests bacterial infection. Prompt immunotherapy after excluding the infectious cause improves long-term outcomes and reduces disability. Post-abortum status may represent a temporal association or potential contributing factor to disease progression, warranting further study and consideration in the differential diagnosis of post-abortum neuropsychiatric syndromes.
Patient perspective
The patient reported that the sudden onset of confusion, memory loss, and seizures was extremely frightening, especially as the initial diagnosis remained unclear. As her condition improved, the patient expressed gratitude for finally understanding the cause of her illness and emphasized the importance of early consideration of autoimmune encephalitis in similar situations. She hopes that sharing her experience will help others receive faster diagnosis and treatment.
What’s new?
This case highlights that anti-NMDAR encephalitis can present with marked neutrophilic CSF pleocytosis, closely mimicking bacterial meningitis and delaying diagnosis. The authors also propose pregnancy termination as a potential immune trigger for disease onset. Clinicians should maintain high suspicion for autoimmune encephalitis in acute neuropsychiatric presentations following abortion.
List of abbreviations
| AE | Autoimmune encephalitis |
| CSF | Cerebrospinal fluid |
| EEG | Electroencephalography / Electroencephalogram |
| GluN1 | Glutamate receptor ionotropic, NMDA 1 subunit |
| ICU | Intensive care unit |
| IgG | Immunoglobulin G |
| IVIG | Intravenous immunoglobulin |
| NMDAR | N-methyl-D-aspartate receptor |
Informed Consent
Written informed consent was obtained from the patient for publication of this case report. The patient reviewed the manuscript and agreed to its submission.
Conflict of interests
The authors declare that there is no conflict of interest regarding the publication of this article.
Funding
None
Consent for publication
Written informed consent was obtained from the patient.
Ethical Approval:
Ethical approval is not required at our institution to publish an anonymous case report.
Author details
Tue Bui Chau1, An Nguyen Thanh1, Loc Le Quang2, Thang Huynh Xuan2, Lap Dinh Van1
- Neurology Department, Cho Ray Hospital, Ho Chi Minh City, Vietnam
- Neurology Department, University of Medicine and Pharmacy at Ho Chi Minh City, Ho Chi Minh City, Vietnam
References
- Dalmau J, Gleichman AJ, Hughes EG, Rossi JE, Peng X, Lai M, et al. Anti-NMDA-receptor encephalitis: case series and analysis of the effects of antibodies. Lancet Neurol. 2008;7(12):1091–8. https://doi.org/10.1016/S1474-4422(08)70224-2
- Armangue T, Spatola M, Vlagea A, Mattozzi S, Cárceles-Cordon M, Martinez-Heras E; Spanish Herpes Simplex Encephalitis Study Group, et al. Frequency, symptoms, risk factors, and outcomes of autoimmune encephalitis after herpes simplex encephalitis: a prospective observational study and retrospective analysis. Lancet Neurol. 2018;17(9):760–72.
- S. Kayser M, Dalmau J. Anti-NMDA Receptor Encephalitis in Psychiatry. Curr Psychiatry Rev. 2011;7(3):189–93.
- Samanta D, Lui F. Anti-NMDAR Encephalitis, in StatPearls. 2025: Treasure Island (FL).
- Nosadini M, Thomas T, Eyre M, Anlar B, Armangue T, Benseler SM, et al. International Consensus Recommendations for the Treatment of Pediatric NMDAR Antibody Encephalitis. Neurol Neuroimmunol Neuroinflamm. 2021;8(5):1052. https://doi.org/10.1212/NXI.0000000000001052
- Schneider R, Brüne M, Breuer T, Börnke C, Gold R, Juckel G. Early Multidisciplinary Intensive-care Therapy can Improve Outcome of Severe Anti-NMDA-receptor Encephalitis Presenting with Extreme Delta Brush. Transl Neurosci. 2019;10(1):241–3. https://doi.org/10.1515/tnsci-2019-0039
- Aleyadeh R, Andrade EIN, Shaikh Z, Bose A, Umeton R. Post-Abortum NMDA Encephalitis (P5-5.010). Neurology. 2023;100(17 supplement_2):4245. https://doi.org/10.1212/WNL.0000000000203845
- SZBSSNFSBFJCe A. Post-Abortum Anti-N-Methyl-D-Aspartate Encephalitis Mimicking Herpetic Encephalitis: a Case Report and Literature Review. J Emergency Med Care. 2021;3:101.
- Doden T, Sekijima Y, Ikeda J, Ozawa K, Ohashi N, Kodaira M, et al. Postpartum Anti-N-methyl-D-aspartate Receptor Encephalitis: a Case Report and Literature Review. Intern Med. 2017;56(3):357–62. https://doi.org/10.2169/internalmedicine.56.7442
- Kumar MA, Jain A, Dechant VE, Saito T, Rafael T, Aizawa H, et al. Anti-N-methyl-D-aspartate receptor encephalitis during pregnancy. Arch Neurol. 2010;67(7):884–7. https://doi.org/10.1001/archneurol.2010.133
- Ciano-Petersen NL, Villagrán-García M, Muñiz-Castrillo S, Farina A, Vogrig A, Goncalves D, et al. Relapses in Anti-NMDAR Encephalitis: clinical Characterization and Predictive Features. Neurol Neuroimmunol Neuroinflamm. 2025;12(4):e200421. https://doi.org/10.1212/NXI.0000000000200421
Summary of the case
| 1 | Patient (gender, age) | 20 years, female |
| 2 | Final diagnosis | Post-abortum NMDA encephalitis |
| 3 | Symptoms | Psychiatry symptoms |
| 4 | Medications | Corticosteroid, IVIg, Rituximab |
| 5 | Clinical procedure | Endotracheal intubation |
| 6 | Specialty | Neurology |
Keywords: Anti-NMDAR encephalitis, autoimmune encephalitis, post-abortum complications, immunotherapy, case report.


Publication History
Received: December 08, 2025
Revised: February 10, 2026
Accepted: February 28, 2026
Published: April 13, 2026
Authors
Tue Bui Chau
Neurology Department, Cho Ray Hospital, Ho Chi Minh City, Vietnam.
An Nguyen Thanh
Neurology Department, Cho Ray Hospital, Ho Chi Minh City, Vietnam.
Loc Le Quang
Neurology Department, University of Medicine and Pharmacy at Ho Chi Minh City, Ho Chi Minh City, Vietnam.
 ORCID
Thang Huynh Xuan
Neurology Department, University of Medicine and Pharmacy at Ho Chi Minh City, Ho Chi Minh City, Vietnam.
Lap Dinh Van
Neurology Department, Cho Ray Hospital, Ho Chi Minh City, Vietnam.