European Journal of Medical Case Reports
Volume 10(8):263–267
Genetic ghosts in the lung: post-COVID fibrosis unveils CTC1 mutation
Christine Azzopardi1*, Joelle Azzopardi2, Peter Fsadni3, Luca Conti4
Correspondence to: Christine Azzopardi
*Higher Specialist Trainee in General Medicine and Respiratory Medicine, Mater Dei Hospital, Msida, Malta.
Email: christine-rose.azzopardi.1@gov.mt
Full list of author information is available at the end of the article.
Received: 22 March 2026 | Revised (1): 06 May 2025 | Accepted: 07 May 2025
ABSTRACT
Background:
Familial pulmonary fibrosis (FPF) accounts for 10%-20% of idiopathic pulmonary fibrosis cases and is associated with mutations in telomere-related genes, including TERT, TERC, RTEL1, PARN, and, more recently, CTC1. Telomere dysfunction predisposes to progressive fibrotic interstitial lung disease (ILD) and may increase susceptibility to environmental triggers. Emerging evidence suggests that COVID-19 pneumonitis may unmask or accelerate fibrosis in genetically predisposed individuals, though a causal relationship has not been established. We report a case of genetically confirmed FPF due to a likely pathogenic CTC1 mutation presenting with progressive post-COVID pulmonary fibrosis.
Case Presentation:
A 59-year-old woman with post-COVID pulmonary fibrosis presented with progressive dyspnea, orthopnea, and functional decline over 6 months. She required long-term oxygen therapy (5 l/min). Family history was significant for two first-degree relatives with usual interstitial pneumonia. Pulmonary function tests showed severe restriction (FVC 48%, diffusing capacity 19%). Imaging evolved from organizing pneumonia during acute COVID-19 to established bilateral fibrotic ILD with traction bronchiectasis and features suggestive of pulmonary hypertension (grade 3), confirmed on right heart catheterization (mean PAP 38 mmHg). Autoimmune workup was largely negative aside from anti-nuclear antibody positivity. Pirfenidone was discontinued due to hepatotoxicity. Genetic testing identified a heterozygous CTC1 variant (c.2518C>T; p.Arg840Trp), classified as likely pathogenic. She was commenced on nintedanib and referred for lung transplantation.
Conclusion:
This case highlights the interplay between telomere-related genetic predisposition and viral injury in FPF. COVID-19 may have unmasked or accelerated fibrotic progression in susceptible individuals, though this association remains observational. Early genetic testing, multidisciplinary management, and timely transplant referral are crucial, with careful monitoring for treatment-related and post-transplant complications.
Keywords:
Pulmonary fibrosis, COVID-19, telomere, CTC1 protein, case report.
Background
Familial pulmonary fibrosis (FPF), defined by interstitial lung disease (ILD) in two or more first-degree relatives, accounts for approximately 10%-20% of idiopathic pulmonary fibrosis (IPF) cases [1-4]. Mutations in telomere-related genes such as TERT, TERC, RTEL1, PARN, and, more recently, CTC1, have been implicated in FPF [5]. The phenotype extends beyond IPF to include a spectrum of potentially progressive pulmonary fibrosis, including idiopathic non-specific interstitial pneumonitis, hypersensitivity pneumonitis, and rheumatoid arthritis-associated ILD [1,2]. Standard management includes antifibrotic therapy (pirfenidone or nintedanib), early multidisciplinary evaluation, genetic counselling in appropriate patients, and timely referral for lung transplantation, which remains the only definitive treatment. Outcomes may be complicated by treatment intolerance and increased risk of post-transplant morbidity in patients with telomere-related gene variants. The COVID-19 pandemic has added complexity, with emerging evidence suggesting viral pneumonitis may unmask or accelerate fibrotic processes in genetically predisposed individuals [6]. We present a case of genetically confirmed FPF with a CTC1 mutation in a patient who developed post-COVID fibrosis and progressive respiratory decline.
Case Presentation
A 59-year-old woman presented with progressive dyspnea at rest, orthopnea, paroxysmal nocturnal dyspnea, and a significant decline in functional capacity over the past 6 months. She had a history of post-COVID pulmonary fibrosis since 2021, initially treated with high-dose steroids and azathioprine. Off-license pirfenidone was trialed but discontinued due to hepatotoxicity as evidenced by a rise in liver transaminases (Table 1).
Table 1. Liver function trends showing a drug-induced liver injury on the introduction of pirfenidone in August 2024.
| REFERENCE RANGE | 03/2024 | 09/2024 | 10/2024 | 11/2024 | 12/2024 | 01/2025 | |
|---|---|---|---|---|---|---|---|
| Bilirubin | 0.0-21 umol/l | 6.9 | 7.0 | 13.1 | 17.2 | 9.7 | 15.8 |
| Alkaline phosphatase | 40-104 U/l | 78 | 166 | 137 | 102 | 123 | 73 |
| Gamma glutamyl transferase | 5-55 U/l | 27 | 609 | 461 | 131 | 137 | 32 |
| Alanine aminotransferase | 14-59 U/l | 24 | 266 | 175 | 77 | 35 | 33 |
Her condition deteriorated following cessation of antifibrotics with the development of fluid overload secondary to right heart failure requiring hospitalization for intravenous diuresis. At presentation, she was on long-term oxygen therapy at 5 l/min continuously and unable to perform basic activities of daily living.
The patient had a strong family history of ILD (Figure 1). Her father passed away at age 80 with IPF [usual interstitial pneumonia (UIP) pattern], and her sister passed away at the age of 52 with respiratory failure secondary to IPF (UIP pattern). There was no family history of consanguinity, liver cirrhosis, or hematological malignancies.
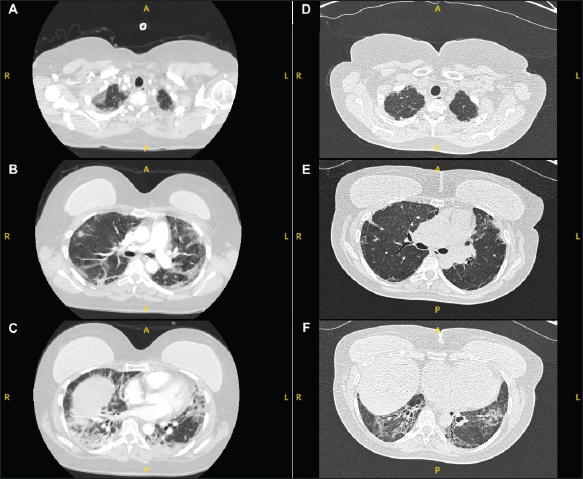
Figure 1. Pedigree chart of the family with FPF: Black and unfilled shapes represent affected and unaffected individuals, respectively. Squares represent males and circles represent females, respectively. The black line running through a circle or square denotes deceased individuals. A small arrow indicates the proband.
Physical examination revealed finger clubbing and bilateral end-inspiratory crackles in the lower and middle lung areas. There was no evidence of nail dystrophy, skin pigmentation changes, or oral leukoplakia.
Pulmonary function tests revealed a restrictive pattern with progressive decline (Forced Vital Capacity declined to 48%, diffusing capacity to 19%). Retrospective assessment of her CT pulmonary artery (CTPA) in 2021 demonstrated bilateral, symmetrical peripheral consolidation and ground glass changes. Confluent consolidation was demonstrated in the lower lobes bilaterally with subpleural sparing (Figure 2A-C). Recent high-resolution CT (HRCT) showed stable, established bilateral fibrosis with lower lobe predominance with evidence of multifocal mid- to lower-zone-predominant thickening of interlobular septa associated with severe traction bronchiectasis, particularly affecting the inferior lingula, middle lobe, and medial segments of bilateral lower lobe (Figure 2D and E). The main pulmonary artery was dilated, measuring 30 mm, in keeping with underlying possible pulmonary hypertension. Echo and right heart catheterization revealed severe right ventricular dysfunction and pulmonary hypertension (mean pulmonary arterial pressure 38 mmHg) consistent with Group 3 pulmonary hypertension due to ILD, as classified by the 2022 ESC/ERS Guidelines, indicating poor prognosis and reinforced the urgency of transplant referral. Due to the patient’s condition, histological verification by transbronchial cryobiopsy was contraindicated, and diagnosis was established on the basis of characteristic HRCT findings, a likely pathogenic CTC1 variant, a strong family history of ILD, and the clinical course.
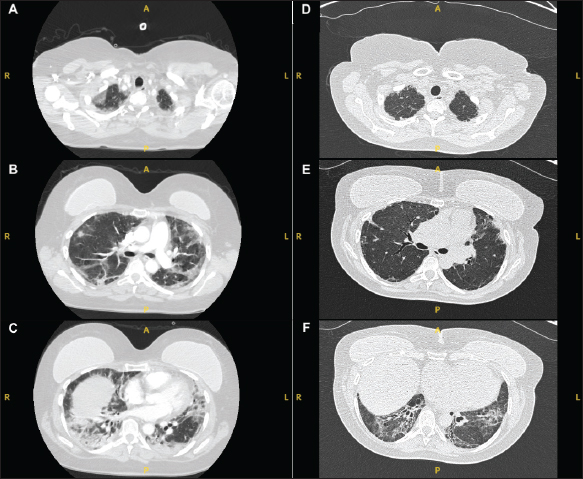
Figure 2. Serial thoracic imaging demonstrating disease progression. (A-C) CTPA in lung window demonstrating bilateral symmetrical peripheral consolidation and ground-glass opacification consistent with organizing pneumonia secondary to COVID-19. Confluent consolidation is visible in the bilateral lower lobes with areas of subpleural sparing. (D-E) HRCT at current presentation demonstrating established bilateral lower-lobe predominant fibrosis with multifocal interlobular septal thickening, severe traction bronchiectasis involving the inferior lingula, middle lobe, and medial segments of the bilateral lower lobes, and a dilated main pulmonary artery measuring 30 mm consistent with pulmonary hypertension.
Autoimmune serology showed anti-nuclear antibody (ANA) positivity but no systemic connective tissue disease (Table 2). Liver function improved following withdrawal of pirfenidone, suggesting drug-induced liver injury (Table 1).
Table 2. Immunology panel.
| TEST | RESULT | REFERENCE RANGE |
|---|---|---|
| ANA | 1/1,000 | |
| ANF pattern | Fine speckled cytoplasmic stain | |
| Extractable nuclear antigen | <1.0 | 0.0-19.0 RU/ml |
| Anti-myeloperoxidase antibody | <2.0 | 0.0-20.0 U/ml |
| Anti-proteinase 3 antibody | <2.0 | 0.0-20.0 U/ml |
| Anti-dsDNA | <10.0 | 0.0-100 IU/ml |
| Rheumatoid factor | <15 | 0.0-15 U/ml |
| Creatinine kinase | 57 | 96-192 U/l |
| Anti-myositis panel: | ||
| Jo-1 Antibodies | Negative | |
| PL-7 Antibodies | Negative | |
| PL-12 Antibodies | Negative | |
| SRP-54 Antibodies | Negative | |
| Ku Antibodies | Negative | |
| MDA-5 antibodies | Negative | |
| Tiff1-gamma antibodies | Negative | |
| EJ antibodies | Negative | |
| PMscl100 antibodies | Negative | |
| PMscl75 antibodies | Negative | |
| OJ antibodies | Positive +++ | |
| Mi2-alpha antibodies | Negative | |
| Mi2-beta antibodies | Negative | |
| NXP2 antibodies | Negative | |
| SAE1 antibodies | Negative | |
| Ro52 antibodies | Negative | |
Genetic testing using CentoXome® Solo by Centogene, Germany, identified a heterozygous CTC1 mutation [NM_025099.5:c.2518C>T, p.(Arg840Trp)], classified as likely pathogenic according to ACMG/AMP criteria, supported by evidence of a deleterious missense change at a conserved residue within a functionally critical domain of CTC1, absence from population databases at disease-relevant frequency, and segregation with ILD in this family. This variant has been previously reported in association with telomere biology disorders and ILD, including in a Chinese family with CTC1-related ILD described by Liu et al. [5], providing additional evidence for its clinical significance. This mutation has been associated with cerebroretinal microangiopathy with calcifications and cysts as well as telomere biology disorders, including pulmonary fibrosis, bone marrow failure, and hepatic dysfunction, reflecting the pleiotropic phenotype of CTC1-STN1-TEN1 complex dysfunction.
Nintedanib was started at the standard dose of 150 mg twice daily after multidisciplinary team discussion and liver function normalization, with observation of liver function tests to avoid a subsequent drug-induced liver injury. The patient was referred to a tertiary center for lung transplant listing, but unfortunately, despite all efforts, the patient passed away in the tertiary center with a massive pulmonary embolism while awaiting transplantation.
Discussion
Telomere integrity is maintained by two essential nucleoprotein complexes - shelterin and the CST complex (comprising CTC1, STN1, and TEN1) - which regulate chromosome end protection and replication. Mutations in these complexes affect telomere maintenance and genome stability, resulting in telomere dysfunction [6,7]. Recent studies have expanded the phenotype associated with CTC1 mutations to include adult-onset fibrotic ILD [5]. The genotype-phenotype correlation for CTC1-related ILD remains incompletely characterized, given the small number of reported cases.
Telomere-related ILDs are characterized by shortened telomeres, accelerated senescence, and increased sensitivity to environmental factors, such as viral infections, smoking, and other unrecognized environmental exposures [8]. Formal telomere length measurement was not performed in this case, representing a key limitation, as objective confirmation would have strengthened the biological plausibility of CTC1-mediated disease. In this patient, COVID-19 infection may have acted as a precipitating factor in the unmasking or acceleration of underlying telomere-mediated fibrosis, though a definitive causal relationship cannot be established from this single case.
Management of FPF with CTC1 mutations is challenging, and a multidisciplinary team should be involved at an early stage. Early genetic diagnosis can aid in risk stratification, guide family screening, and inform transplant candidacy [1-3]. Antifibrotics, such as pirfenidone and nintedanib, may slow disease progression, but tolerance in these patients is often limited by systemic side effects. In this case, pirfenidone was discontinued following hepatotoxicity, which is a recognized adverse effect and typically reversible on withdrawal. Nintedanib, on the other hand, has a lower hepatotoxic burden at therapeutic doses and therefore was selected in the case.
The European Respiratory Society task force on FPF recommends considering genetic sequencing for diagnosing fibrotic ILD patients who have at least one first- or second-degree relative also affected by fibrotic ILD, carry a known familial variant, show features of short telomere syndrome, or are diagnosed with idiopathic fibrosing ILD before the age of 50 years to help clarify potential hereditary causes [2].
Lung transplantation remains the only definitive intervention, but it is complicated by comorbidities and poor functional status. Patients with pathogenic TRG variants, such as our patient with a CTC1 mutation, are at increased risk of adverse outcomes following lung transplantation [9]. These include a higher incidence of infections and greater susceptibility to drug-related toxicities [4]. Notably, they are particularly vulnerable to severe hematological complications, especially bone marrow failure requiring cautious use of immunosuppressive therapy [10,11]. There is also a high incidence of acute renal failure and acute tubular necrosis. Immunosuppressive and antimicrobial regimens, including mycophenolate, calcineurin inhibitors, and cytotoxic agents, are associated with toxicities including hepatotoxicity [10,12]. Infectious complications, including sepsis as well as opportunistic infections such as pulmonary aspergillosis and cytomegalovirus pneumonitis [10,13].
Psychosocial aspects also play a critical role [14]. Our patient, unable to work or leave the house, expressed significant emotional distress and existential concerns. A multidisciplinary approach involving pulmonology, genetics, psychology, and palliative care is essential [15]. The fatal outcome in this case represents an important and sobering learning point with several clinically plausible contributing factors, including profound immobility related to continuous oxygen dependence, advanced fibrotic ILD, and the presence of group 3 pulmonary hypertension.
This case is strengthened by comprehensive clinical, radiological, hemodynamic, and genetic characterization, including identification of a likely pathogenic CTC1 variant in a patient with a strong family history of ILD, thereby contributing to the limited literature on CST complex-related pulmonary fibrosis and its potential interaction with COVID-19-associated lung injury. The temporal association between viral pneumonitis and fibrotic progression provides clinically relevant insight into possible gene-environment interplay in telomere-mediated disease, though causality cannot be established and is observational. Histopathological confirmation was not obtained as transbronchial cryobiopsy was contraindicated, representing a meaningful diagnostic limitation. Nonetheless, diagnostic confidence remains supported by characteristic HRCT appearance, CTC1 variant, strong family history of pulmonary fibrosis, and a compatible clinical trajectory. As a single case report, causality between COVID-19 and disease acceleration cannot be definitively established.
Conclusion
This case illustrates the complex interactions between genetic predisposition and environmental triggers in FPF. The presence of a pathogenic CTC1 mutation underscores the need for genetic screening in patients with a suggestive family history. COVID-19 pneumonitis may have unmasked or accelerated disease in susceptible individuals, though this remains an association rather than an established causal mechanism. Early recognition, multidisciplinary care, and consideration of lung transplantation are vital in optimizing outcomes in these patients. Due to the high risk of complications, hematological and renal monitoring is highly recommended.
What is new?
The authors report a case of genetically confirmed CTC1-associated FPF in which COVID-19 pneumonitis may have unmasked or accelerated underlying telomere-mediated fibrosis. It illustrates the potential for viral triggers to expose latent genetic susceptibility in ILD and highlights that early genetic testing - even in the absence of a classic telomere biology disorder phenotype - can be pivotal in establishing diagnosis, guiding antifibrotic and transplant decision making an enabling family screening.
List of Abbreviations
| ANA | Anti-nuclear antibody |
| CTPA | CT pulmonary artery |
| DLCO | Diffusing capacity |
| FPF | Familial pulmonary fibrosis |
| HRCT | High-resolution CT |
| ILD | Interstitial lung disease |
| IPF | Idiopathic pulmonary fibrosis |
| UIP | Usual interstitial pneumonia |
Conflict of interests
The authors declare that there is no conflict of interest regarding the publication of this article.
Funding
None.
Consent for publication
Written informed consent was obtained from the patient.
Ethical approval
Ethical approval is not required at our institution to publish an anonymous case report.
Author details
Christine Azzopardi1, Joelle Azzopardi2, Peter Fsadni3, Luca Conti4
- Higher Specialist Trainee in General Medicine and Respiratory Medicine, Mater Dei Hospital, Msida, Malta
- Internal Medicine and Respiratory Consultant, Gozo General Hospital, Victoria, Malta
- Internal Medicine and Respiratory Consultant, Mater Dei Hospital, Msida, Malta
- Resident Specialist in General Medicine and Respiratory Medicine, Mater Dei Hospital, Msida, Malta
References
- Borie R, Kannengiesser C, Nathan N, Tabèze L, Pradère P, Crestani B. Familial pulmonary fibrosis. Rev Mal Respir. 2015;32(4):413–34. https://doi.org/10.1016/j.rmr.2014.07.017
- Borie R, Kannengiesser C, Antoniou K, Bonella F, Crestani B, Fabre A, et al. European Respiratory Society statement on familial pulmonary fibrosis. Eur Respir J. 2023;61(3):2201383. https://doi.org/10.1183/13993003.01383-2022
- Kropski JA, Young LR, Cogan JD, Mitchell DB, Lancaster LH, Worrell JA, et al. Genetic evaluation and testing of patients and families with idiopathic pulmonary fibrosis. Am J Respir Crit Care Med. 2017;195(11):1423–8. https://doi.org/10.1164/rccm.201609-1820PP
- Moen EV, Prior TS, Kreuter M, Wuyts WA, Molina-Molina M, Wijsenbeek M, et al. Diagnosis, screening, and follow-up of patients with familial interstitial lung disease: results from an international survey. BMC Pulmonary Med. 2025;25(1):59. https://doi.org/10.1186/s12890-025-03532-0
- Liu L, Luo H, Sheng Y, Kang X, Peng H, Luo H, et al. A novel mutation of CTC1 leads to telomere shortening in a Chinese family with interstitial lung disease. Hereditas. 2023;160:37. https://doi.org/10.1186/s41065-023-00299-4
- John AE, Joseph C, Jenkins G, Tatler AL. COVID-19 and pulmonary fibrosis: a potential role for lung epithelial cells and fibroblasts. Immunol Rev. 2021;302(1):228–40. https://doi.org/10.1111/imr.12977
- De Lange T. Shelterin: the protein complex that shapes and safeguards human telomeres. Genes Dev. 2005;19(18):2100–10. https://doi.org/10.1101/gad.1346005
- Wellinger RJ. The CST complex and telomere maintenance: the exception becomes the rule. Mol Cell. 2009;36(2):168–9. https://doi.org/10.1016/j.molcel.2009.10.001
- Kropski JA, Pritchett JM, Zoz DF, Crossno PF, Markin C, Garnett ET, et al. Extensive phenotyping of individuals at risk for familial interstitial pneumonia reveals clues to the pathogenesis of interstitial lung disease. Am J Respir Crit Care Med. 2015;191(4):417–26.
- Borie R, Le Guen P, Ghanem M, Taillé C, Dupin C, Dieudé P, et al. The genetics of interstitial lung diseases. Eur Respir Rev. 2019;28(153):190053. https://doi.org/10.1183/16000617.0053-2019
- Borie R, Kannengiesser C, Hirschi S, Le Pavec J, Mal H, Bergot E, et al. Severe hematologic complications after lung transplantation in patients with telomerase complex mutations. J Heart Lung Transplant. 2015;34(4):538–46. https://doi.org/10.1016/j.healun.2014.11.010
- Silhan LL, Shah PD, Chambers DC, Snyder LD, Riise GC, Wagner CL, et al. Lung transplantation in telomerase mutation carriers with pulmonary fibrosis. Eur Respir J. 2014;44(1):178–87. https://doi.org/10.1183/09031936.00060014
- Tokman S, Singer JP, Devine MS, Westall GP, Aubert JD, Tamm M, et al. Clinical outcomes of lung transplant recipients with telomerase mutations. J Heart Lung Transplant. 2015;34(10):1318–24. https://doi.org/10.1016/j.healun.2015.05.002
- Zhang D, Newton CA. Familial pulmonary fibrosis: genetic features and clinical implications. Chest. 2021;160(5):1764–73. https://doi.org/10.1016/j.chest.2021.06.037
- Franco G, Ba I, Nathan N, Guerin C, Lassus A, Kannengiesser C, et al. Impact of A multidisciplinary team discussion for genetic lung fibrosis. Respirology. 2025;30(6):523–32. https://doi.org/10.1111/resp.70039
Summary of case
| 1 | Patient (gender, age) | 53 years, male |
| 2 | Final diagnosis | Non-traumatic ISDH in a patient with polycythemia vera |
| 3 | Symptoms | Right arm weakness progressing to right leg weakness and dysarthria |
| 4 | Medications | Prior on: Acetylsalicylic acid, hydroxyurea; chronic phlebotomy program |
| 5 | Clinical procedure | Emergency craniotomy and evacuation of SDH; intensive care management |
| 6 | Specialty | Internal medicine/Hematology/Neurosurgery |
Keywords: Pulmonary fibrosis, COVID-19, telomere, CTC1 protein, case report.


Publication History
Received: March 22, 2026
Revised: May 06, 2026
Accepted: May 07, 2026
Published: July 25, 2026
Authors
Christine Azzopardi
Higher Specialist Trainee in General Medicine and Respiratory Medicine, Mater Dei Hospital, Msida, Malta.
Joelle Azzopardi
Internal Medicine and Respiratory Consultant, Gozo General Hospital, Victoria, Malta.
Peter Fsadni
Internal Medicine and Respiratory Consultant, Mater Dei Hospital, Msida, Malta.
Luca Conti
Resident Specialist in General Medicine and Respiratory Medicine, Mater Dei Hospital, Msida, Malta.