European Journal of Medical Case Reports
Volume 10(7):218–222
Systemic disease associations and management of pyoderma gangrenosum: a single-center retrospective case series
Ilyas El Kassimi1* , Adil Rkiouak1, Nawal Sahel1, Meryem Zaizaa1, Zineb El Bougrini1, Bilal Talamoussa1, Youssef Sekkach1
Correspondence to: Ilyas El Kassimi
*Department of Internal Medicine, Mohammed V Military Teaching Hospital, Mohammed V University, Rabat, Morocco.
Email: dr.elkassimiilyas@gmail.com
Full list of author information is available at the end of the article.
Received: 18 February 2026 | Revised (1): 08 March 2026 | Revised (2): 10 March 2026 | Accepted: 06 April 2026
ABSTRACT
Background:
Pyoderma gangrenosum (PG) is a rare neutrophilic dermatosis frequently associated with systemic inflammatory diseases. We aimed to describe systemic disease associations, management strategies, and outcomes of PG managed in internal medicine.
Settings:
Single-center retrospective case series conducted in an internal medicine department between January 2021 and December 2025.
Methods:
We retrospectively reviewed all eligible patients treated for PG in our department during the study period. Diagnosis was based on clinicopathological assessment after exclusion of major mimickers; the Delphi consensus criteria were not formally applied because their individual components were not consistently documented in the retrospective records. Demographic, clinical, histological, treatment, and outcome data were extracted from medical records.
Results:
Ten patients (five women; median age 40 years, range 19-58) were included. Ulcerative PG predominated (6/10), while four patients had pustular PG; lesions mainly involved the lower limbs, and pathergy was observed in five patients. An associated systemic disease was identified in eight patients, including Behçet disease, inflammatory bowel disease, systemic sclerosis, anti-neutrophil cytoplasmic antibody-associated vasculitis, systemic lupus erythematosus, and Takayasu arteritis. All patients received systemic corticosteroids; additional immunosuppressants or anti-tumor necrosis factor-alpha therapy were used as steroid-sparing treatment and/or to control active associated systemic disease. Six patients achieved complete healing without relapse, whereas four experienced at least one relapse during chart-documented follow-up.
Conclusion: In internal medicine practice, PG is commonly linked to systemic inflammatory diseases, supporting a structured, clinically guided systemic work-up. Systemic corticosteroids remain first-line therapy, while immunosuppressants and targeted biologics are valuable steroid-sparing options when disease is refractory or coexists with active systemic inflammation.
Keywords:
Pyoderma gangrenosum, neutrophilic dermatoses, systemic inflammatory diseases, autoimmune diseases, corticosteroids, biologic therapy.
Background
Pyoderma gangrenosum (PG) is a rare neutrophilic dermatosis characterised by painful inflammatory skin lesions, most often ulcerations with violaceous undermined borders [1-3]. Although primarily cutaneous, PG frequently occurs in a systemic context, with an associated disease reported in up to half of cases in published series, including inflammatory bowel disease, inflammatory arthritis, and hematologic disorders [4,5]. The management of PG remains challenging because of its heterogeneous presentations, the absence of a pathognomonic diagnostic test, and the need to exclude mimickers such as infection, vasculitis, and malignancy [1,6,7]. Diagnostic frameworks such as the Delphi consensus criteria are useful for standardization, but their retrospective application may be limited when some items are not systematically documented [6]. Therapeutic evidence is mainly derived from case series and observational studies; systemic corticosteroids and ciclosporin are commonly used, and biologic therapies, particularly anti-tumor necrosis factor (TNF)-alpha agents, are increasingly reported in refractory disease [2,8,9]. Internal medicine plays a key role in the diagnosis and comprehensive assessment of PG because of its systemic associations. We therefore report a case series of PG managed in an internal medicine department, focusing on clinical features, associated systemic diseases, treatment strategy, and outcomes.
Patients and Methods
Study design and setting: Retrospective descriptive observational study conducted in an internal medicine department. Patient identification and selection: Cases were identified through review of departmental inpatient and outpatient records between January 2021 and December 2025. Patients were included if they had a final diagnosis of PG and sufficient clinical, histological, treatment, and outcome data for analysis; records lacking essential data were excluded. Diagnostic approach: PG was diagnosed on clinico-pathological grounds based on a compatible painful ulcerative or pustular presentation, exclusion of major alternative diagnoses (infection, vasculitis, malignancy), and supportive histology when available. Skin biopsy was used primarily to rule out infectious, vasculitic, or malignant causes and, when compatible, to support the diagnosis of neutrophilic dermatosis. Because of the retrospective design and incomplete documentation of all individual items, Delphi consensus criteria were not formally applied. Data collection: Data were extracted from medical records using a standardized form including demographics; past medical and surgical history; PG characteristics (onset, subtype, number, size, localization, pain, pathergy); laboratory and histological findings; associated systemic diseases; treatments (local and systemic); and outcomes (healing, relapse, follow-up documentation). Laboratory and systemic assessment: All patients underwent a basic laboratory work-up, including blood count, inflammatory markers, renal and liver function tests, serum protein electrophoresis, and viral serologies. Beyond routine laboratory tests, the systemic work-up was clinically guided according to the presentation and included, when indicated, autoimmune testing [for example ANA, anti-dsDNA and anti-neutrophil cytoplasmic antibody (ANCA)], evaluation for hematologic disease, gastrointestinal assessment in patients with digestive symptoms, and symptom-directed imaging or specialist referral. Outcome definitions: Complete healing was defined as full re-epithelialization of all active PG lesions. Relapse was defined as the recurrence of clinically compatible PG after complete healing. Outcomes were assessed from chart-documented follow-up visits. Because follow-up duration was not uniformly recorded across all files, a reliable cohort-level median and range of follow-up could not be calculated. Statistical analysis: Data are presented descriptively as n (%) or median (range), as appropriate.
Results
Demographics: Ten patients were included (five women and five men), with a median age of 40 years (range 19–58). Clinical presentation: Disease onset was progressive in most cases. Lesions were constantly painful, typically presenting as painful ulcerations with a fibrino-necrotic base and raised violaceous borders (Figure 1). Ulcerative PG was the most frequent subtype (6/10), while four patients presented with pustular PG (Table 1). Lesions mainly involved the lower limbs, followed by the upper limbs and, less commonly, the trunk. Pathergy was observed in five patients, including lesions arising on surgical scars or after minor trauma (Figure 2). Laboratory and histology: Several patients had inflammatory anaemia and/or neutrophilic leukocytosis. Inflammatory markers were variably elevated (Table 2). Histology most often showed a neutrophil-predominant inflammatory infiltrate without specific evidence of vasculitis; biopsy was mainly useful to exclude differential diagnoses. Associated systemic diseases: An associated systemic disease was identified in eight patients (80%): Behçet disease (n = 2), inflammatory bowel disease (Crohn’s disease, n = 1), systemic sclerosis (n = 2), systemic lupus erythematosus (n = 1), ANCA-associated vasculitis (n = 1), and Takayasu arteritis (n = 1) (Table 1). Treatment and outcomes: All patients received systemic corticosteroids. Escalation to conventional immunosuppressants (methotrexate, azathioprine, cyclophosphamide) and/or anti-TNF-alpha therapy was undertaken in selected patients because of insufficient response to corticosteroids, slow healing or relapsing disease, and/or the need to control an active associated systemic disease (Table 3). Six patients achieved complete healing without relapse, whereas four experienced at least one relapse during chart-documented follow-up. Because follow-up duration was heterogeneous and incompletely documented in some charts, relapse rates should be interpreted cautiously.
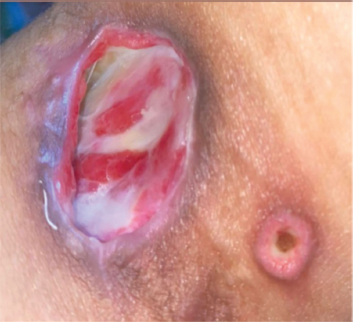
Figure 1. Painful lower-limb ulcer with a fibrino-necrotic base and raised violaceous undermined borders, clinically typical of ulcerative PG.
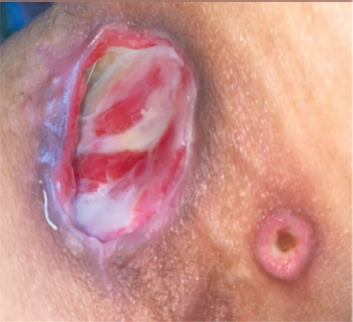
Figure 2. Upper-limb PG occurring on a postsurgical scar and after an insect bite, illustrating pathergy and the need to avoid unnecessary trauma.
Table 1. Baseline clinical characteristics of patients with PG (n = 10).
| PATIENT | AGE (YEARS) | SEX | PG SUBTYPE | COMORBIDITIES | NUMBER OF LESIONS | MAIN LOCALIZATION |
|---|---|---|---|---|---|---|
| 1 | 37 | Female | Ulcerative | Raynaud phenomenon; systemic sclerosis; hypertension | 1 | Anterior aspect of right leg |
| 2 | 19 | Male | Ulcerative | Systemic lupus erythematosus | 3 | Anterior aspect of left leg |
| 3 | 45 | Female | Ulcerative | Systemic sclerosis; Raynaud phenomenon | 3 | Lateral aspect of left leg |
| 4 | 58 | Male | Pustular | Current smoker | 12 | Dorsum of hand; left elbow; knees; abdomen |
| 5 | 43 | Male | Ulcerative | Angio-Behçet disease | 1 | Medial aspect of left leg |
| 6 | 24 | Female | Ulcerative | None reported | 2 | Medial aspect of elbow |
| 7 | 50 | Female | Pustular | ANCA-associated vasculitis | Multiple (>3) | Right leg |
| 8 | 28 | Male | Pustular | Fistulising Crohn’s disease; current smoker | 1 | Lateral aspect of right ankle |
| 9 | 24 | Female | Pustular | Takayasu arteritis | 1 | Left leg |
| 10 | 44 | Male | Ulcerative | Behçet disease; current smoker | 1 | Anterior aspect of right leg |
Abbreviations: PG, pyoderma gangrenosum.
Table 2. Summary of laboratory findings.
| CASE | BLOOD COUNT | CRP / ESR | RENAL FUNCTION (UREA/CREATININE) | LIVER TESTS | SERUM PROTEIN ELECTROPHORESIS | VIRAL SEROLOGIES |
|---|---|---|---|---|---|---|
| 1 | Normal | CRP normal; ESR normal | Normal | Normal | Normal | Negative |
| 2 | Normal | CRP normal; ESR normal | Normal | Normal | Normal | Negative |
| 3 | Normal | CRP normal; ESR normal | Normal | Normal | Normal | Negative |
| 4 | Normal | CRP 42 mg/l; ESR 35 mm/h | Normal | Normal | Moderate inflammatory pattern | Negative |
| 5 | Hb 9.6 g/dl | CRP normal; ESR normal | Normal | Normal | Inflammatory pattern | Negative |
| 6 | Neutrophilic leukocytosis | CRP 30 mg/l; ESR 56 mm/h | Normal | Normal | Normal | Negative |
| 7 | Neutrophilic leukocytosis; Hb 10.8 g/dl | CRP 30 mg/l; ESR 60 mm/h | Normal | Mild cholestasis | Inflammatory pattern | Negative |
| 8 | Neutrophilic leukocytosis; Hb 11.1 g/dl | CRP 70 mg/l; ESR 100 mm/h | Normal | Normal | Inflammatory pattern | Negative |
| 9 | Hb 9.2 g/dl (WBC normal) | CRP 60 mg/l; ESR 70 mm/h | Normal | Transaminases 1.5 × ULN | Inflammatory pattern | Negative |
| 10 | Neutrophilic leukocytosis (Hb normal) | CRP 10 mg/l; ESR 20 mm/h | Normal | Normal | Normal | Negative |
Abbreviations: Hb, haemoglobin; WBC, white blood cell count; CRP, C-reactive protein; ESR, erythrocyte sedimentation rate; ULN, upper limit of normal.
Table 3. Systemic treatments and rationale for therapeutic escalation in patients with PG.
| PATIENT | SEX | AGE (YEARS) | COMORBIDITY | SYSTEMIC TREATMENT | RATIONALE FOR ADJUVANT THERAPY |
|---|---|---|---|---|---|
| 1 | Female | 37 | Raynaud phenomenon; systemic sclerosis; hypertension | Systemic corticosteroids + methotrexate + azathioprine + colchicine | No improvement with corticosteroids alone |
| 2 | Male | 19 | Systemic lupus erythematosus | Systemic corticosteroids | — |
| 3 | Female | 45 | Systemic sclerosis; Raynaud phenomenon | Systemic corticosteroids | — |
| 4 | Male | 58 | Current smoker | Systemic corticosteroids | — |
| 5 | Male | 43 | Behçet disease | Systemic corticosteroids + methotrexate + anti-TNF-alpha + colchicine | No improvement with corticosteroids alone; treat underlying Behçet disease |
| 6 | Female | 24 | None reported | Systemic corticosteroids | — |
| 7 | Female | 50 | ANCA-associated vasculitis | Systemic corticosteroids + cyclophosphamide | Treat ANCA-associated vasculitis |
| 8 | Male | 28 | Fistulising Crohn’s disease | Systemic corticosteroids + azathioprine + anti-TNF-alpha | Slow healing; treat underlying Crohn’s disease |
| 9 | Female | 24 | Takayasu arteritis | Systemic corticosteroids | — |
| 10 | Male | 44 | Behçet disease | Systemic corticosteroids + anti-TNF-alpha | No improvement with corticosteroids alone; treat underlying Behçet disease |
Abbreviations: TNF-alpha, tumor necrosis factor alpha.
Discussion
This study illustrates the polymorphic nature of PG and underscores the central role of internal medicine in recognising systemic associations and coordinating management [1,2]. The balanced sex distribution observed in our cohort differs from some reports suggesting a slight female predominance, but sex ratios vary widely across published series [4,5]. A key finding is the high frequency of associated systemic diseases (80%). This proportion appears higher than the approximately 50% association rate generally reported in population-based or dermatology-led series [4,5], and may reflect the case mix of an internal medicine referral setting, where patients with multisystem inflammatory disease are overrepresented. These findings support a structured, but clinically guided, search for inflammatory, autoimmune, and autoinflammatory disorders in patients with PG, particularly when the presentation is atypical, recurrent, or treatment-refractory [1,5]. Diagnosis remains challenging because no single clinical, histological, or laboratory feature is pathognomonic. In our practice, diagnosis relied on the combination of a typical painful ulcerative or pustular lesion, exclusion of infection, vasculitis, and malignancy, and supportive biopsy findings when available. Although the Delphi consensus criteria provide a useful standardized framework, they were not formally applied retrospectively because not all items were consistently documented in the medical records [6]. Pathergy, observed in half of our patients, is an important clinical clue and has practical implications for avoiding unnecessary surgical procedures and for careful wound care [7,9]. Therapeutically, systemic corticosteroids were used in all cases, consistent with their role as first-line therapy [8,9]. Escalation beyond corticosteroids was considered in cases with inadequate early response, slow healing, relapsing or multifocal disease, or when additional control of an active associated systemic disease was required. In this setting, the choice of adjuvant therapy was individualised according to comorbidity profile and the need for steroid-sparing treatment. Anti-TNFa therapy was used in patients with Behçet disease or Crohn’s disease, reflecting a pragmatic strategy that targeted both PG and the associated inflammatory disorder [2]. Overall outcomes were favorable, although relapses occurred in a substantial proportion of patients, in line with previous reports [4]. Limitations include the retrospective single-center design, the small sample size, and the lack of uniformly documented follow-up duration, which limits the precise interpretation of relapse rates. Nevertheless, our findings provide practical insights relevant to internal medicine, where PG is often encountered in complex systemic contexts.
Conclusion
In this single-center internal medicine case series, PG was frequently associated with systemic inflammatory diseases and required multidisciplinary management. Diagnosis relied on careful exclusion of mimickers and clinico-pathological correlation. Systemic corticosteroids were used in all patients, while additional immunosuppressants and anti-TNF-alpha agents were valuable steroid-sparing options, particularly when PG coexisted with active systemic disease. These findings support a structured, clinically guided systemic work-up in patients with PG.
What is new?
In a single-centre retrospective case series managed in an internal medicine department, the authors found systemic disease associations in 80% of patients, spanning a broad spectrum of inflammatory and autoimmune disorders. They describe practical diagnostic clues (including pathergy) and real-world management patterns showing that treatment choices were guided by both PG severity and the underlying systemic disease, including the use of anti-TNFα agents as steroid-sparing therapy in selected patients.
Acknowledgment
We thank all healthcare professionals involved in the care of the patients. We also thank Professor A.R and Professor Y.S for their support and supervision during the preparation of this work.
List of Abbreviations
| ANCA | Anti-neutrophil cytoplasmic antibodies |
| CRP | C-reactive protein |
| ESR | Erythrocyte sedimentation rate |
| IBD | Inflammatory bowel disease |
| PG | Pyoderma gangrenosum |
| TNF-alpha | Tumor necrosis factor alpha |
Conflict of interest
The authors declare that there is no conflict of interest regarding the publication of this article.
Funding
None.
Consent for publication
Written informed consent for publication of clinical images was obtained from the relevant patients; consent forms are archived by the authors. For this retrospective analysis of de-identified routine-care data, additional individual informed consent was not required according to institutional policy.
Ethical approval
This study was conducted in accordance with the Declaration of Helsinki. Because this retrospective study analyzed anonymized routine-care data, formal ethics committee approval was not required under institutional policy and applicable regulations.
Data sharing
No additional data are available.
Author details
Ilyas El Kassimi1, Adil Rkiouak1, Nawal Sahel1, Meryem Zaizaa1, Zineb El Bougrini1, Bilal Talamoussa1, Youssef Sekkach1
- Department of Internal Medicine, Mohammed V Military Teaching Hospital, Mohammed V University, Rabat, Morocco
References
- Alavi A, French LE, Davis MD, Brassard A, Kirsner RS. Pyoderma gangrenosum: an update on pathophysiology, diagnosis and treatment. Am J Clin Dermatol. 2017;18(3):355–72. https://doi.org/10.1007/s40257-017-0251-7
- Fletcher J, Alhusayen R, Alavi A. Recent advances in managing and understanding pyoderma gangrenosum. F1000 Res. 2019;8:F1–19. https://doi.org/10.12688/f1000research.19909.1
- Braswell SF, Kostopoulos TC, Ortega-Loayza AG. Pathophysiology, diagnosis, and treatment of pyoderma gangrenosum. Dermatol Ther. 2015;28:348–55.
- Binus AM, Qureshi AA, Li VW, Winterfield LS. Pyoderma gangrenosum: a retrospective review of patient characteristics, comorbidities and therapy in 103 patients. Br J Dermatol. 2011;165(6):1244–50. https://doi.org/10.1111/j.1365-2133.2011.10565.x
- Langan SM, Groves RW, Card TR, Gulliford MC. Incidence, mortality, and disease associations of pyoderma gangrenosum in the United Kingdom: a retrospective cohort study. J Invest Dermatol. 2012;132(9):2166–70. https://doi.org/10.1038/jid.2012.130
- Maverakis E, Ma C, Shinkai K, Fiorentino D, Callen JP, Wollina U, et al. Diagnostic criteria of ulcerative pyoderma gangrenosum: a Delphi consensus of international experts. JAMA Dermatol. 2018;154(4):461–6. https://doi.org/10.1001/jamadermatol.2017.5980
- Su WPD, Davis MDP, Weenig RH, Powell FC, Perry HO. Pyoderma gangrenosum: clinicopathologic correlation and proposed diagnostic criteria. Int J Dermatol. 2004;43(11):790–800. https://doi.org/10.1111/j.1365-4632.2004.02128.x
- Reichrath J, Bens G, Bonowitz A, Tilgen W. Treatment recommendations for pyoderma gangrenosum: an evidence-based review of the literature based on more than 350 patients. J Am Acad Dermatol. 2005;53(2):273–83. https://doi.org/10.1016/j.jaad.2004.10.006
- Brooklyn T, Dunnill G, Probert C. Diagnosis and treatment of pyoderma gangrenosum. BMJ. 2006;333(7560):181–4. https://doi.org/10.1136/bmj.333.7560.181
Keywords: Pyoderma gangrenosum, neutrophilic dermatoses, systemic inflammatory diseases, autoimmune diseases, corticosteroids, biologic therapy.


Publication History
Received: February 18, 2026
Revised: March 08, 2026 Revised: March 10, 2026
Accepted: April 06, 2026
Published: June 19, 2026
Authors
Ilyas El Kassimi
Department of Internal Medicine, Mohammed V Military Teaching Hospital, Mohammed V University, Rabat, Morocco.
 ORCID
Adil Rkiouak
Department of Internal Medicine, Mohammed V Military Teaching Hospital, Mohammed V University, Rabat, Morocco.
Nawal Sahel
Department of Internal Medicine, Mohammed V Military Teaching Hospital, Mohammed V University, Rabat, Morocco.
Meryem Zaizaa
Department of Internal Medicine, Mohammed V Military Teaching Hospital, Mohammed V University, Rabat, Morocco.
Zineb El Bougrini
Department of Internal Medicine, Mohammed V Military Teaching Hospital, Mohammed V University, Rabat, Morocco.
Bilal Talamoussa
Department of Internal Medicine, Mohammed V Military Teaching Hospital, Mohammed V University, Rabat, Morocco.
Youssef Sekkach
Department of Internal Medicine, Mohammed V Military Teaching Hospital, Mohammed V University, Rabat, Morocco.