European Journal of Medical Case Reports
Volume 10(6):188–189
Type 1 Brugada-electrocardiogram after therapeutic doses of propafenone for atrial fibrillation. A true Brugada syndrome or Brugada phenocopy?
Ioannis A. Vogiatzis1* , Evangelos Sdogkos1, Aggelos Georgakopoulos1
Correspondence to: Ioannis A. Vogiatzis
*Cardiologist, Department of Cardiology, General Hospital of Veroia, Veroia, Greece.
Email: ivogia@hotmail.gr
Full list of author information is available at the end of the article.
Received: 18 December 2025 | Revised (1): 08 February 2026 | Accepted: 19 February 2026
This case report presents a 25-year-old man with paroxysmal atrial fibrillation (Figure 1A) who developed a transient Type 1 Brugada Electrocardiogram (ECG) pattern following a single 300 mg oral dose of propafenone for rhythm control (Figure 1B). The patient had a CHA2DS2-VASc score of 0 and was not on anticoagulation at the time of propafenone administration. Characteristic coved ECG interval-segment elevation developed within 45 minutes of the drug administration and had resolved by the following day (Figure 1C). He experienced a syncopal episode, later attributed to a positive tilt test of vasodepressor type and not primary arrhythmia. Further investigations, including a negative flecainide provocative test, a non-inducible electrophysiological study (using pacing from the right ventricular apex and outflow tract with up to three extra stimuli at two drive cycles), and negative genetic testing for SCN5A mutation (the only gene tested in this clinical context), excluded true congenital Brugada syndrome. The lack of a personal or family history of sudden cardiac death led the ECG changes to be considered to represent a Brugada phenocopy: a drug-induced manifestation unmasked by the sodium channel blocker propafenone.
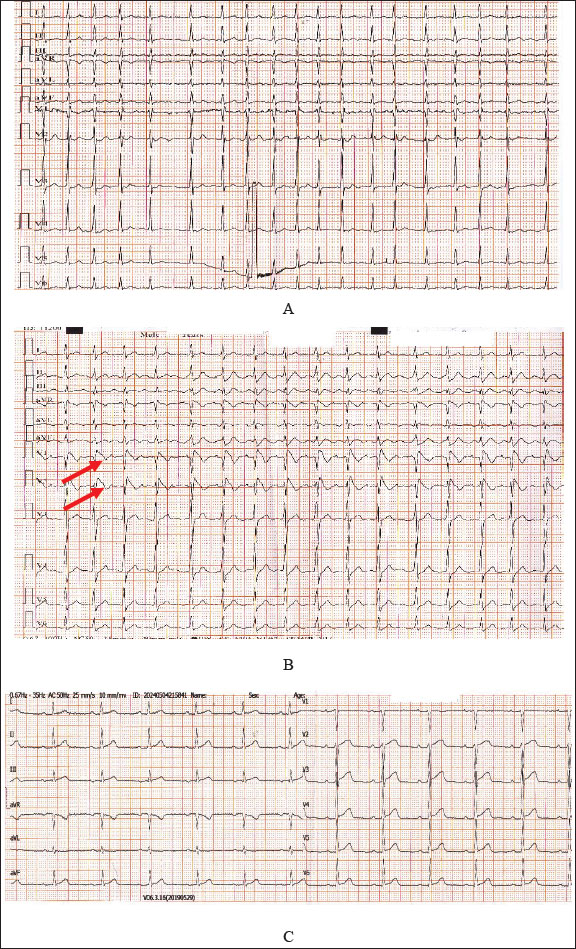
Figure 1. ECG course. This sequential ECG series illustrates a fully reversible, drug-induced Brugada phenocopy unmasked by sodium channel blockade with propafenone. A: ECG of patient’s admission to the hospital showing rapid atrial fibrillation. The morphology of QRS is normal without any significant ST-T changes. B: ECG 45 minutes after propafenone (300 mg) administration. Standard precordial lead placement was used. Typical type 1 Brugada pattern is visible in V1-V2, highlighted with arrows. C: ECG recorded the next day before the discharge of the patient from the hospital.
The therapeutic dosage of propafenone may unmask the Brugada pattern and recognition, along with appropriate risk stratification, is warranted to distinguish this Brugada phenocopy from the genuine inherited syndrome. It is important to note that Brugada-like ECG patterns are dynamic and can be unmasked not only by sodium channel blockers, but also by fever, increased vagal tone, and other factors, all of which should be considered in the evaluation. The patient remained asymptomatic with no Atrial fibrillation recurrence at 3-month follow-up.
Keywords:
Atrial fibrillation, propafenone, Brugada syndrome, Brugada phenocopy.
Conflicts of interest
The authors declare that they have no conflict of interest regarding the publication of this case report.
Funding
None.
Informed consent
Written consent was obtained from the patient.
Ethical approval
Ethical approval is not required at our institution to publish an anonymous case report.
Author details
Ioannis A. Vogiatzis1, Evangelos Sdogkos1, Aggelos Georgakopoulos1
- Cardiologist, Department of Cardiology, General Hospital of Veroia, Veroia, Greece
Keywords: Atrial fibrillation, propafenone, Brugada syndrome, Brugada phenocopy.


Publication History
Received: February 18, 2025
Revised: February 08, 2026
Accepted: February 19, 2026
Published: May 05, 2026
Authors
Ioannis Vogiatzis
Cardiologist, Department of Cardiology, General Hospital of Veroia, Veroia, Greece.
 ORCID
Evangelos Sdogkos
Cardiologist, Department of Cardiology, General Hospital of Veroia, Veroia, Greece.
Aggelos Georgakopoulos
Cardiologist, Department of Cardiology, General Hospital of Veroia, Veroia, Greece.