European Journal of Medical Case Reports
Volume 10(7):214–217
Intralobar pulmonary sequestration in an adult patient: a case report
Amin Abdelsalam1* , Aya Doudin1
Correspondence to: Amin Abdelsalam
*Cleveland Clinic, Abu Dhabi, United Arab Emirates.
Email: abdulsa4@ccad.ae
Full list of author information is available at the end of the article.
Received: 28 January 2026 | Revised (1): 13 March 2026 | Accepted:20 April 2026
ABSTRACT
Background:
Pulmonary sequestration (PS) is a rare congenital lung anomaly in which non-functioning lung tissue receives a systemic arterial supply. While typically diagnosed in childhood, adult presentation, especially of the intralobar type, remains uncommon and often challenging to recognize.
Case Presentation:
We report the case of a 46-year-old woman who presented to the emergency department with acute dry cough, dyspnea, and a single episode of hemoptysis. She had no prior history of pulmonary infections or chronic illness aside from untreated hypertension. Laboratory results were unremarkable apart from a mildly elevated D-dimer (0.6 mcg/ml). Imaging via computed tomography angiography revealed a mass-like consolidation with systemic arterial supply from the aorta and pulmonary venous drainage, consistent with intralobar pulmonary sequestration. The patient was admitted for observation and remained clinically stable without recurrent hemoptysis or infection. She was discharged with outpatient cardiothoracic follow-up and remained asymptomatic at follow-up visits.
Conclusion:
This case highlights the importance of considering intralobar pulmonary sequestration in adults with atypical respiratory symptoms and unexplained hemoptysis. Although surgical resection is typically recommended, particularly for symptomatic cases or those with recurrent infections, our patient’s favorable course with conservative management supports the potential for individualized, non-operative strategies in selected asymptomatic adults. Further long-term data in adult populations are needed to decide optimal treatment decisions.
Keywords:
Pulmonary sequestration, lung diseases, congenital, hemoptysis, dyspnea, tomography, X-ray computed angiography.
Introduction
Pulmonary sequestration (PS), also known as bronchopulmonary sequestration, is characterized by a non-functioning lung tissue that receives blood supply from systemic arteries. PS is a rare congenital disorder, with an estimated incidence of 2.2%-6.6%. PS, however, is considered the second most common congenital lung anomaly [1,2].
PS is classified, based on pleural covering of the additional lung tissue, into two subtypes: extralobar pulmonary sequestration (ELPS) and intralobar pulmonary sequestration (ILPS). The ELPS is separated from normal lung tissue by a distinct visceral pleura. ILPS is incorporated within normal lung tissue and covered by its visceral pleura [3,4]. Patients with PS can be asymptomatic or can present with cough, fever, hemoptysis, or chest pain; thus, making the diagnosis difficult unless a high index of suspicion is present. Most patients with PS present as cases of recurrent pulmonary infections, though some are found incidentally on imaging [5].
Case Presentation
A 46-year-old Asian female patient presented to the emergency department with worsening dry cough and shortness of breath for one day. She also reported having one episode of severe cough and hemoptysis described as a single clot. She denied any fever, chills, chest pain, weight loss, night sweats, neurological symptoms, or history of lung infection or tuberculosis. She had no medical history except for hypertension, for which she was not taking any medications. She denied the possibility of pregnancy. Physical examination revealed an elevated blood pressure of 188/107; other vitals were within normal limits. Chest exam revealed equal air entry bilaterally without added sounds. Neurological and abdominal examinations were unremarkable.
The patient’s laboratory results revealed an elevated D-dimer level at 0.6, but other laboratory values, including CBC, CMP, CRP, Troponin, BNP, TSH, and VBG, were unremarkable.
- Hemoglobin: 129 g/dl
- White blood cell count: 9.2 ×10⁹/l
- Platelet count: 359 ×109/l
- C-reactive protein: 0.8 mg/l
- D-dimer: 0.6 mcg/ml (mildly elevated).
Chest x-ray was reported as normal cardiomedisatinal silhouette with evidence of lung lesions. CT angiography showed a left lower lobe tree-in-bud nodularity and masslike consolidation in the posterior basal segment, measuring approximately 35mm x 30mm. The lesion was supplied by an anomalous systemic artery arising from the descending thoracic aorta. The feeding artery measured approximately 7 mm in diameter and originated from the descending thoracic aorta at the T8 vertebral level. Venous drainage was observed through the left inferior pulmonary vein into the left atrium. No communication with the tracheobronchial tree was identified. These imaging findings were consistent with intralobar pulmonary sequestration (Figure 1).
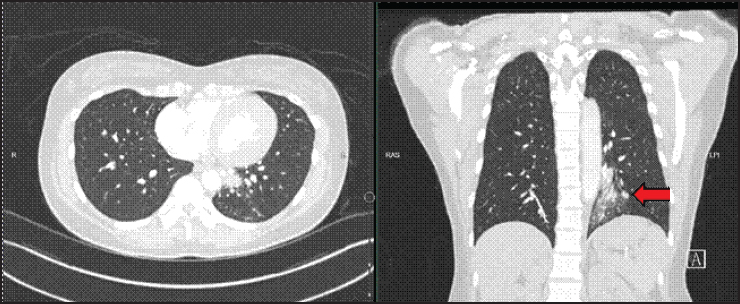
Figure 1. Axial and coronal sections of CT angiography scan demonstrating a masslike consolidation in the posterior basal segment of the left lower lobe (arrow). An anomalous systemic artery arising from the descending thoracic aorta supplies the lesion, consistent with intralobar pulmonary sequestration.
The patient was admitted to the hospital for observation of recurrence of hemoptysis or lung infection. In the same CT scan, the patient was found to have an adrenal mass incidentally. The mass was measured to be 3.7 x 4.2 mm in dimensions. It was resected the following month, and pathology revealed pheochromocytoma. During her admission for surgery, the patient was counselled about the benefits of surgery for the pulmonary sequestration, but she opted to wait. The patient’s hospital stay was uneventful, and she was eventually discharged with cardiothoracic surgery follow-up. She was seen at the cardiothoracic surgery clinic and was completely asymptomatic and did not have lung infection or recurrence of hemoptysis after discharge. She was discharged with follow-up in 3 and 6 months, and strict return precautions for lung infection.
Discussion
PS is a rare congenital disease of the respiratory system that describes a mass of lung tissue receiving arterial supply from sources other than the pulmonary arteries. The exact cause of pulmonary sequestration has been a subject of debate for many years, with many theories proposed as the etiology of pulmonary sequestration. The most widely accepted theory is accessory budding of lung tissue that is caudal to the normal lung tissue [1,6]. A retrospective study of 72 patients diagnosed with PS found that intralobar PS was more common than extralobar PS (92.8% vs. 7.2%). The population studied was mainly adults with a mean age of 36.6 years. It was also reported that intralobar PS was 2-fold more common to be localized to the left lower lung lobe than the right lung [7]. The study also highlighted that 22.7% of cases were asymptomatic and found incidentally, but common presentations varied between cough, chest pain, hemoptysis, and fever. Chest computed tomography with angiography was diagnostic in only 37.5% of patients, indicating frequent missing or misdiagnosis of PS on CTA [7].
A study looking at pediatric patients with PS (mean age 20 months) reported that intralobar pulmonary sequestrations most commonly were supplied by branches from aberrant arteries originating from the thoracic or abdominal aorta [8]. Moreover, it was found that intralobar PS common venous drainage was via the pulmonary arteries, keeping in line with our patient from this case report. The study suggested that video-assisted thoracic surgery was a safe and efficacious modality for resection of intralobar pulmonary sequestration, with results that could be equally effective and safe for adult patients with PS [8, 9].
A retrospective comparative study of 28 patients aimed to emphasize key differences between adult and pediatric PS [10]. It was found that 91% of patients with intralobar PS had recurrent infections as opposed to 14% in patients with extralobar PS. Additionally, the study also reported that adults with PS experienced more respiratory infections when compared with children with PS (87% vs. 38%). Furthermore, adult patients more frequently required lobectomy in contrast to the pediatric population (67% vs. 31%). Early surgical intervention was advised whenever pulmonary malformations were diagnosed in adults to prevent recurrent chest infections and enhance parenchymal-sparing lung resections [9,10]. The patient in this case report was treated conservatively with observation and outpatient follow-ups due to lack of PS complications and frequent infections.
Surgical resection is traditionally considered the preferred treatment for pulmonary sequestration, particularly in symptomatic patients or those with recurrent infections, due to risks of hemoptysis, infection, and, rarely, malignant transformation [11]. However, recent reports suggest that conservative management may be reasonable in selected adult patients who remain asymptomatic or minimally symptomatic [12,13]. In the present case, the patient experienced only a single episode of hemoptysis and remained clinically stable without recurrence during follow-up. Therefore, a non-operative approach with careful surveillance was considered appropriate.
A suggested treatment modality of PS is endovascular embolization. A retrospective study of pediatric patients compared outcomes of surgical resection, endovascular embolization, and observation [14]. Surgical resection was mainly done for patients with recurrent infections, and endovascular embolization was done for patients with left-to-right shunts. Although embolization and resection were associated with favorable outcomes overall, patients who were observed without treatment did not have any major complications, but they were asymptomatic at the time of diagnosis (no left-to-right shunt or pulmonary infection) [14,15]. These findings may justify the conservative management used in our case, but the study has limited evidence of long-term data and only studied pediatric patients.
Conclusion
Intralobar pulmonary sequestration still remains a rare but important differential diagnosis to consider in adults presenting with atypical respiratory symptoms, particularly hemoptysis and recurrent infections. This case report emphasizes that intralobar pulmonary sequestration can remain asymptomatic until adulthood and may be incidentally discovered or misdiagnosed due to its variable presentation. While surgical resection remains the standard of care for symptomatic or complicated cases, conservative management with close monitoring may be appropriate for select asymptomatic adults, especially in patients where the lesion is discovered incidentally and without evidence of recurrent infection or hemodynamic compromise. However, given the relatively short follow-up of our patient, the suggestion of conservative management must be interpreted with caution. Further studies, more specifically in the adult population, are needed to better define the long-term outcomes of nonoperative management and to guide individualized treatment strategies in patients with pulmonary sequestration.
What is new?
Pulmonary sequestration is a rare congenital lung anomaly characterized by non-functioning lung tissue with systemic arterial supply. Intralobar sequestration is the more common subtype and is typically located in the left lower lobe. Although presentations vary, many cases are asymptomatic or incidentally detected, and diagnosis can be challenging, as CT angiography may miss or misidentify the condition.
Conflict of interests
The authors declare that there is no conflict of interest regarding the publication of this article.
Funding
None.
Consent for publication: (Applicable to case reports only)
Due permission was obtained from the patient to publish the case and the accompanying images.
Ethical approval
Ethical approval is not required at our institution to publish an anonymous case report.
Author details
Amin Abdelsalam1, Aya Doudin1
- Cleveland Clinic , Abu Dhabi, United Arab Emirates
References
- Corbett HJ, Humphrey GM. Pulmonary sequestration. Paediatr Respir Rev. 2004;5(1):59–68. https://doi.org/10.1016/j.prrv.2003.09.009
- Muri J, Makovicky P, Kamarad V, Durcova B, Vecanova J, Hvizdosova N. Pulmonary sequestration in adulthood: clinical-morphological study. Bratisl Lek Listy. 2024;125(3):153–8. https://doi.org/10.4149/BLL_2023_140
- Wei Y, Li F. Pulmonary sequestration: a retrospective analysis of 2625 cases in China. Eur J Cardiothorac Surg. 2011;40(1):e39–42. https://doi.org/10.1016/j.ejcts.2011.01.080
- Ren S, Yang L, Xiao Y, Tong Z, Wang L, Hu Y. Pulmonary sequestration in adult patients: a single-center retrospective study. Respir Res. 2023;24(1):36635696. https://doi.org/10.1186/s12931-023-02320-w
- Petersen G, Martin U, Singhal A, Criner GJ. Intralobar sequestration in the middle-aged and elderly adult: recognition and radiographic evaluation. J Thorac Cardiovasc Surg. 2003;126(6):2086–90. https://doi.org/10.1016/S0022-5223(03)01297-2
- Chakraborty RK, Modi P, Sharma S. Pulmonary Sequestration[Updated 2023 Jul 24] StatPearls [Internet]Treasure Island (FL): StatPearls Publishing; 2025, Available from https://www.ncbi.nlm.nih.gov/sites/books/NBK532314
- Sun X, Xiao Y. Pulmonary sequestration in adult patients: a retrospective study. Eur J Cardiothorac Surg. 2015;48(2):279–82. https://doi.org/10.1093/ejcts/ezu397
- Zhang N, Zeng Q, Chen C, Yu J, Zhang X. Distribution, diagnosis, and treatment of pulmonary sequestration: report of 208 cases. J Pediatr Surg. 2019;54(7):1286–92. https://doi.org/10.1016/j.jpedsurg.2018.08.054
- Trabalza Marinucci B, Maurizi G, Vanni C, Cardillo G, Poggi C, Pardi V, et al. Surgical treatment of pulmonary sequestration in adults and children: long-term results. Interact Cardiovasc Thorac Surg. 2020;31(1):71–7. https://doi.org/10.1093/icvts/ivaa054
- Van Raemdonck D, De Boeck K, Devlieger H, Demedts M, Moerman P, Coosemans W, et al. Pulmonary sequestration: a comparison between pediatric and adult patients. Eur J Cardiothorac Surg. 2001;19(4):388–95. https://doi.org/10.1016/S1010-7940(01)00603-0
- Halkic N, Cuénoud PF, Corthésy ME, Ksontini R, Boumghar M. Pulmonary sequestration: a review of 26 cases. Eur J Cardiothorac Surg. 1998;14(2):127–33. https://doi.org/10.1016/S1010-7940(98)00154-7
- Robson VK, Shieh HF, Wilson JM, Buchmiller TL. Non-operative management of extralobar pulmonary sequestration: a safe alternative to resection?. Pediatr Surg Int. 2020;36(3):325–31. https://doi.org/10.1007/s00383-019-04590-2
- Song JY, Park SG, Lee HY, Kim SR, Kim HG, Shin SH, et al. Comparison of clinical outcomes of pulmonary sequestration in adults between surgery and non-surgery groups. J Thorac Dis. 2022;14(10):3876–85. https://doi.org/10.21037/jtd-22-631
- Brown SC, Dch F, Laat MD, Proesmans M, Boeck KD, Raemdonck DV, et al. Treatment strategies for pulmonary sequestration in childhood: resection, embolization, observation?. Acta Cardiol. 2012;67(6):629–34. https://doi.org/10.1080/AC.67.6.2184664
- Cho MJ, Kim DY, Kim SC, Kim KS, Kim EAR, Lee BS. Embolization versus surgical resection of pulmonary sequestration: clinical experiences with a thoracoscopic approach. J Pediatr Surg. 2012;47(12):2228–33. https://doi.org/10.1016/j.jpedsurg.2012.09.013
Summary of the case
| 1 | Patient (gender, age) | A 46-year-old female patient |
| 2 | Final Diagnosis | Intralobar pulmonary sequestration |
| 3 | Symptoms | Dry cough, dyspnea, hemoptysis (single episode) |
| 4 | Medications | None reported (patient not on antihypertensive treatment) |
| 5 | Clinical Procedure | CT angiography (diagnostic); conservative management (observation and follow-up) |
| 6 | Specialty | Emergency Medicine / Pulmonology / Cardiothoracic Surgery |
Keywords: Pulmonary sequestration, lung diseases, congenital, hemoptysis, dyspnea, tomography, X-ray computed angiography.


Publication History
Received: January 28, 2026
Revised: March 13, 2026
Accepted: April 20, 2026
Published: June 19, 2026
Authors
 ORCID
Aya Doudin
Cleveland Clinic , Abu Dhabi, United Arab Emirates.