European Journal of Medical Case Reports
Volume 10(6):177–181
Leiomyoma of the bladder dome mimicking a urachal remnant managed with robotic partial cystectomy: a case report
Eylon J. Arbel1* , Elias Atri1, Yaeli Bierman2, Robert Poppiti2,3, Leonardo D. Borregales1
Correspondence to: Eylon J. Arbel
*Columbia University Division of Urology, Mount Sinai Medical Center, Miami Beach, FL.
Email: eylon.arbel@msmc.com
Full list of author information is available at the end of the article.
Received: 19 December 2025 | Revised (1): 22 March 2026 | Accepted: 10 April 2026
ABSTRACT
Background:
Bladder leiomyoma is an uncommon, benign, smooth-muscle neoplasm that can closely resemble a urachal remnant when located at the anterior bladder or dome. Imaging findings may overlap substantially with urachal remnants or other lesions, and definitive diagnosis often requires surgical excision, especially in symptomatic patients or when malignancy cannot be excluded. Bladder leiomyoma arising at the bladder dome is particularly uncommon and may radiographically mimic a urachal remnant, creating diagnostic uncertainty and affecting preoperative decision-making.
Case Presentation:
A 45-year-old woman presented with approximately 6 months of suprapubic discomfort and progressive stress-predominant urinary incontinence. Pelvic magnetic resonance imaging demonstrated a 3 cm anterior/dome lesion favored to represent a urachal remnant. Cystoscopy showed an invaginating dome mass with intact mucosa, limiting the utility of transurethral biopsy. Given persistent symptoms, nondiagnostic imaging, and the inability to exclude a urachal remnant, the patient underwent robotic-assisted partial cystectomy with en bloc excision of the dome lesion and a short urachal margin. Intraoperative frozen section suggested a benign process, and final histopathology confirmed a leiomyoma. The postoperative course was uncomplicated, and the patient recovered without issues.
Conclusion:
Leiomyoma of the bladder dome can clinically and radiographically resemble urachal remnants, leading to diagnostic uncertainty when the mucosa is intact and imaging is equivocal. In symptomatic patients where a urachal remnant or malignancy cannot be excluded, robotic partial cystectomy provides both definitive diagnosis and symptom relief with minimal morbidity. This case underscores the importance of considering benign, smooth-muscle tumors in the differential diagnosis of anterior/dome lesions.
Keywords:
Leiomyoma, bladder cancer, urachal remnant, cystectomy, robotic surgery.
Background
Leiomyoma of the urinary bladder is an uncommon benign, non-epithelial tumor, comprising a small fraction of bladder neoplasms [1,2]. Lesions arising in the bladder dome or anterior wall can closely mimic urachal anomalies, including cysts, sinuses, diverticula, and rarely adenocarcinoma on cross-sectional imaging and cystoscopic evaluation [3,4]. Diagnostic ambiguity is increased when the mucosal surface appears intact over a superficial or intramural mass, limiting the yield of cystoscopic biopsy and favoring a management strategy that secures both diagnosis and therapy. In such scenarios, clinicians must consider the limited specificity of imaging for urachal processes and the small but meaningful malignant potential within the urachal disease spectrum. We present a symptomatic dome lesion favored preoperatively to be urachal in origin that proved to be a leiomyoma on pathologic evaluation, managed via robotic partial cystectomy [5-7].
Case Report
A 45-year-old woman with prior thyroid cancer, surgical management of cervical dysplasia, two cesarean deliveries, and appendectomy presented with approximately 6 months of suprapubic discomfort and progressive urinary incontinence. This began as stress-predominant and evolved to mixed incontinence without provocation, including nocturnal episodes requiring frequent use of absorbent pads. She denied gross hematuria, fever, flank pain, and weight loss. She was a never-smoker and reported no family history of genitourinary malignancy.
Office urinalysis from a prior visit demonstrated pyuria and bacteriuria with squamous epithelial cells; urine culture subsequently showed no growth. Serum creatinine was 0.66 mg/dl (estimated glomerular filtration rate ~110 ml/min/1.73 m²). Bladder-washing cytology was negative for high-grade urothelial carcinoma. A renal/bladder ultrasound was nondiagnostic.
Pelvic magnetic resonance imaging (MRI) demonstrated a 3 cm lesion in the anterior bladder dome, reported as suspicious for a urachal remnant (Figure 1). She was referred to our urology office, where flexible cystoscopy identified the mass invaginating at the dome without an obvious mucosal origin; the overlying urothelium appeared intact, and ureteral orifices were orthotopic with clear efflux. The constellation of a midline/dome lesion, intact mucosa, and MRI impression of a urachal remnant supported anterior dome pathology rather than a papillary urothelial tumor. The working differential included urachal cyst, patent urachus, urachal sinus or vesicourachal diverticulum, urachal abscess, and (less likely) urachal adenocarcinoma. After discussing risks, side effects, and alternatives, surgical excision was favored over transurethral resection as symptoms may have been caused by the lesion, imaging and cystoscopy favored a urachal remnant, and urachal malignancy could not be excluded. Furthermore, the lesion was deemed to be unresectable via a transurethral approach, which supported robotic partial cystectomy, expected to be both diagnostic and therapeutic.
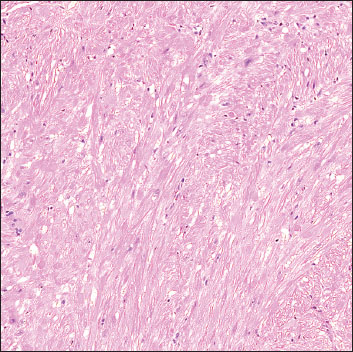
Figure 1. Pelvic MRI: Axial/Sagittal view bladder lesion. The image shown includes an axial and sagittal view of a pelvic MRI demonstrating a 3 cm anterior/dome lesion suspicious of a urachal remnant.
The patient underwent robotic-assisted laparoscopic partial cystectomy with planned excision of the dome lesion and urachal remnant. Four 8 mm robotic trocars were placed in a transverse line, with an assistant port between the camera and right-hand trocar. Dorsal lithotomy and steep Trendelenburg facilitated excellent pelvic exposure. The space of Retzius was developed to mobilize the anterior bladder and track the medial umbilical ligaments toward the bladder dome. A cystoscope was briefly introduced to confirm intravesical topography and aid with the selection of the bladder entry point. A limited cystotomy was created, and the lesion, measuring approximately 3 cm and invaginating toward the lumen, was excised en bloc with a cuff of the dome and an additional medial umbilical ligament margin. The cystotomy (approximately 5 cm) was closed in two layers with barbed suture, incorporating mucosa internally and imbricating detrusor/serosa externally. A standardized backfill of 150-200 ml confirmed a watertight repair. An 18 Fr 2-way Foley catheter was left to dependent drainage, and a small closed-suction drain was placed prophylactically. Hemostasis was excellent, and port sites were closed with absorbable suture and skin adhesive.
Pathological examination revealed a well-circumscribed, tan-white, whorled, bulging nodule measuring 1.5 × 1.3 × 1.0 cm. Intraoperative frozen section evaluation favored a benign process. Permanent sections showed a well-circumscribed smooth-muscle neoplasm, composed of intersecting fascicles of uniform spindle cells exhibiting abundant eosinophilic cytoplasm and elongated, blunt-ended (“cigar-shaped”) nuclei without significant atypia or mitotic activity, diagnostic of a leiomyoma of the urinary bladder (Figures 2 and 3). Surgical margins were negative. The immediate postoperative course was uncomplicated. Pain was well-controlled, oral intake was tolerated, and she ambulated on postoperative day 0 and was discharged home on postoperative day 1. Early follow-up and discussion with the patient revealed an interval increase in bladder spasms, likely due to acute Foley catheter irritation, well-controlled with Ditropan and Levsin. The Foley catheter was removed 2 weeks postoperatively, and the cystogram was negative for any filling defects or perivesical extravasation of contrast. The patient was prescribed Solifenacin as needed. She was also counseled that bladder leiomyoma is a benign condition with an excellent prognosis after complete excision; any persistent stress-predominant incontinence would be evaluated separately [1-7].
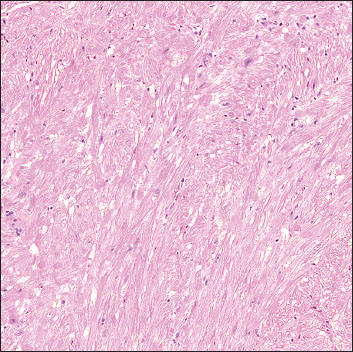
Figure 2. 10× Hematoxylin & eosin stain. The image demonstrates a 10× hematoxylin and eosin stain demonstrating a neoplastic lesion beneath the urothelium composed of intersecting fascicles of uniform spindle cells.
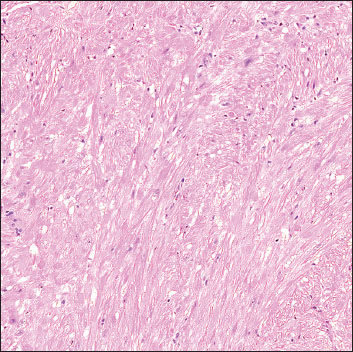
Figure 3. 20× Hematoxylin & eosin stain. The image demonstrates a 20× hematoxylin and eosin stain demonstrating a neoplasm composed of spindle cells exhibiting abundant eosinophilic cytoplasm and elongated, blunt-ended (“cigar-shaped”) nuclei without significant atypia or mitotic activity.
Discussion
Adult urachal anomalies are uncommon and can present heterogeneously with suprapubic pain, irritative voiding symptoms, umbilical discharge, hematuria, or discovery of a midline mass [3,4]. Imaging is central to assessment, and a prevesical midline cyst on computed tomography (CT) or a T2-hyperintense tract on MRI may suggest a urachal remnant. However, the specificity of cross-sectional imaging is limited, especially in the presence of inflammation or when lesions abut the anterior bladder wall. Moreover, when a process is superficial or intramural, cystoscopy may reveal intact urothelium with a subtle invagination or bulge, a picture that does not readily distinguish urachal disease from a neoplasm such as leiomyoma [1,2]. These overlapping features explain why in adults with meaningful symptoms and a surgically approachable midline/dome lesion, definitive excision is often preferred over surveillance and conservative management.
The management decision in this case hinged on three factors. First, the patient’s symptom burden was substantial, with stress-predominant leakage progressing to unprovoked episodes and enuresis. Addressing the structural lesion may provide improved quality of life irrespective of final histology. Although the relationship between the dome lesion and the patient’s urinary symptoms remains uncertain, it was believed that the lesion may have altered bladder compliance or stimulated local parasympathetic activity, contributing to irritative symptoms. Second, although MRI favored a urachal remnant, neither imaging nor cystoscopy provided diagnostic certainty. Biopsy can be nondiagnostic when the mucosa is intact, and the lesion resides within the detrusor; furthermore, for suspected urachal malignancy, aggressive cystoscopic resection at the dome is often avoided due to theoretical concerns about tumor seeding and suboptimal oncologic control in a location not easily encompassed cystoscopically [3]. Third, while most urachal remnants in adults are benign, the literature documents rare but aggressive urachal adenocarcinoma and even malignant transformation in lesions initially thought benign, underscoring the appropriate decision of early excision in selected symptomatic adults [3,4].
Bladder leiomyoma itself is a benign, smooth-muscle neoplasm that may be intramural, subserosal, or within the lamina propria [1,2,5,6,7]. Presenting symptoms reflect size and location: irritative voiding complaints, pelvic pressure, obstructive symptoms with trigonal proximity, or, less commonly, hematuria. Imaging typically demonstrates a well-circumscribed mass with relative homogeneity compared with urothelial carcinoma, but histopathology remains the diagnostic gold standard. Histologically, they are composed of intersecting fascicles of uniform spindle cells exhibiting abundant eosinophilic cytoplasm and elongated, blunt-ended (“cigar-shaped”) nuclei without significant atypia or mitotic activity. Immunohistochemically, the tumor cells demonstrate strong and diffuse positivity for smooth muscle actin (SMA), desmin, and caldesmon, supporting their smooth muscle differentiation [5-7]. This diagnosis was established on routine hematoxylin-eosin morphology, and immunohistochemistry was not required in this case as the histologic features were classic for leiomyoma. Smooth muscle markers such as SMA, desmin, and caldesmon may be used when diagnostic uncertainty exists. No evidence of a urachal remnant or malignancy was identified in the resected specimen. When small and intravesical, cystoscopic resection may suffice; for intramural or subserosal lesions, particularly in the dome or anterior wall, partial cystectomy is favored to achieve complete excision and durable symptom relief [1,2].
This case highlights several clinically relevant novel features. First, the leiomyoma developed at the bladder dome in a location typically associated with a urachal remnant, as seen on imaging findings. Second, the intact mucosal surface limited the diagnostic value of cystoscopic biopsy and was deemed unresectable via a transurethral approach, creating a preoperative diagnostic challenge. Finally, the patient had a symptom profile with quality-of-life-limiting factors that could not be ignored. This drove us toward a robotic-assisted partial cystectomy, which was deemed to be a minimally invasive approach that provided both diagnostic and therapeutic benefits with limited comorbidities. This case report has several limitations. The first is the relatively short follow-up duration, as patient-reported outcomes were not available following the catheter removal appointment at 2 weeks and the 4-week follow-up after this appointment, although the patient was satisfied in the postoperative period. Furthermore, to our knowledge, this is one of the only symptomatic suspected urachal remnant cases to be managed with robotic partial cystectomy. The outcomes of this case may not be generalizable to a majority of patients with this pathology. Lastly, robotic partial cystectomy is not universally available at all medical centers.
The literature describes leiomyomas that develop in various locations in the bladder. For instance, both cases reported by Bangash et al. [1] describe leiomyomas of the bladder that developed on the left lateral wall, and the case reported by He et al. [2] describes a leiomyoma that developed on the right posterior wall. However, in a case very similar to ours, Stanescu et al. [5] report a 1 cm soft tissue thickening at the bladder dome in a 53-year-old female with lower urinary tract symptoms that was initially thought to be consistent with a urachal remnant on CT imaging. She underwent subsequent transurethral resection, and final pathology demonstrated a benign leiomyoma [5]. This variety showcases the unpredictable nature of leiomyoma tumorigenesis in the bladder and how they can mimic urachal remnants when coincidentally formed at the bladder dome. It also demonstrates that definitive management with minimally invasive robotic surgery can provide both diagnostic and therapeutic benefits to the patient when both imaging is nondiagnostic, and symptom burden is significant.
Conclusion
A symptomatic anterior/dome bladder mass with intact mucosa and imaging suggestive of a urachal remnant may, on final pathology, prove to be a benign, smooth-muscle tumor. When urachal disease cannot be excluded preoperatively, and symptoms are clinically significant, robotic partial cystectomy offers definitive diagnosis and durable symptom relief with favorable recovery.
What is new?
Bladder leiomyoma arising at the bladder dome can closely mimic urachal pathology when the overlying mucosa is intact, creating a diagnostic challenge in which imaging and cystoscopy may be inconclusive.
List of Abbreviations
| MRI | Magnetic resonance imaging |
| CT | Computed tomography |
| LUTS | Lower urinary tract symptoms |
Conflict of interests
The authors declare that there is no conflict of interest regarding the publication of this article.
Funding
None.
Consent for publication
Written informed consent was obtained from the patient.
Ethical approval
Ethical approval is not required at our institution to publish an anonymous case report.
Author details
Eylon J. Arbel1, Elias Atri1, Yaeli Bierman2, Robert Poppiti2,3, Leonardo D. Borregales1
- Columbia University Division of Urology, Mount Sinai Medical Center, Miami Beach, FL
- Department of Pathology, Mount Sinai Medical Center, Miami Beach, FL
- Department of Pathology, Herbert Wertheim College of Medicine, Florida International University, Miami, FL
References
Summary of case
| 1 | Patient (gender, age) | 45 years, female |
| 2 | Final diagnosis | Leiomyoma of the urinary bladder |
| 3 | Symptoms | Urinary incontinence |
| 4 | Medications | Ditropan, Levsin, and Solifenacin following operative management |
| 5 | Clinical procedure | Robotic-assisted partial cystectomy |
| 6 | Specialty | Urologic oncology |
Keywords: Leiomyoma, bladder cancer, urachal remnant, cystectomy, robotic surgery.


Publication History
Received: December 19, 2025
Revised: March 22, 2026
Accepted: April 10, 2026
Published: May 05, 2026
Authors
Eylon J Arbel
Columbia University Division of Urology, Mount Sinai Medical Center, Miami Beach, FL.
 ORCID
Elias Atri
Columbia University Division of Urology, Mount Sinai Medical Center, Miami Beach, FL.
Yaeli Bierman
Department of Pathology, Mount Sinai Medical Center, Miami Beach, FL.
Robert Poppiti
Department of Pathology, Mount Sinai Medical Center, Miami Beach, FL.
Leonardo D. Borregales
Columbia University Division of Urology, Mount Sinai Medical Center, Miami Beach, FL.