European Journal of Medical Case Reports
Volume 10(5):136–142
A case report unmasking two functional cases of non-obstructive coronary artery disease in the young: two mechanisms and one diagnostic key
Naqiya Arsiwala1 , Abhisheka Tripathi2*, Binal Raj3, Divyesh Dadhania4
Correspondence to: Abhisheka Tripathi
*Department of Cardiology, Zydus Hospitals and Healthcare Research Private Limited, Ahmedabad, India.
Email: drabhishekatripathi@gmail.com
Full list of author information is available at the end of the article.
Received: 20 November 2025 | Revised (1): 16 February 2026 | Accepted: 04 March 2026
ABSTRACT
Background:
Ischemia with Non-obstructive Coronary Arteries (INOCA), historically considered benign, is now recognized as a cause of recurrent angina, functional limitation, and adverse cardiovascular outcomes. In some patients, it may progress to myocardial infarction with non-obstructive coronary arteries (MINOCA). Recognition in younger individuals remains limited, contributing to a delay in diagnosis and treatment.
Case Presentation:
Patient 1: A 16-year-old previously healthy male presented with paroxysmal palpitations and chest discomfort at rest. Nine months later, recurrent symptoms were accompanied by transient ST-segment depression on serial electrocardiography and elevated high-sensitivity troponin I (614 ng/l). Coronary angiography showed unobstructed epicardial vessels. Cardiac magnetic resonance (CMR) revealed focal subendocardial late gadolinium enhancement in the basal inferolateral wall consistent with vasospasm-induced myocardial infarction. Patient 2: A 34-year-old man reported four months of exertional chest discomfort and dyspnea on exertion with normal serial electrocardiography and troponin. Coronary angiography revealed normal epicardial vessels. Adenosine stress CMR identified diffuse subendocardial perfusion defects with quantitatively reduced myocardial blood flow (1.54 ml/min/g) consistent with global microvascular dysfunction.
Conclusion:
These cases underscore that INOCA can affect young individuals without traditional risk factors, and that CMR offers definitive diagnostic and prognostic value when invasive angiography is non-contributory.
Keywords:
INOCA/MINOCA, cardiac MRI, vasomotor dysfunction, vasospastic angina, young patients
Introduction
Ischemia with Non-Obstructive Coronary Arteries (INOCA) is a clinical syndrome where objective myocardial ischemia occurs despite the absence of obstructive disease (stenosis < 50%), a finding broadly categorized as NOCAD (Non-Obstructive Coronary Artery Disease). Contemporary evidence demonstrates that 40% to 70% of patients undergoing coronary angiography for angina demonstrate no obstructive epicardial disease, with approximately 80 % meeting the INOCA diagnostic criteria [1-3].
According to the 2024 ESC Guidelines, INOCA is a distinct entity driven by coronary vasomotor dysfunction, manifesting via two primary endotypes: Coronary Microvascular Dysfunction (CMD) and Epicardial Vasospasm [4,5]
Epicardial vasospasm produces transient, dynamic obstruction in otherwise normal appearing arteries, while CMD involves structural and/or functional abnormalities of small intramyocardial vessels impairing myocardial perfusion [5]. Previously considered benign, INOCA now shows increased risk of major adverse cardiovascular events, including progression to heart failure, myocardial infarction, and sudden death [6]. INOCA and MINOCA likely exist on a shared pathophysiological continuum wherein prolonged spasm may result in myocardial necrosis [7].
Epidemiologically, INOCA is most described in middle-aged women, but recognition in younger, otherwise healthy patients, including adolescents remains exceedingly rare [3,8].
Conventional diagnostic modalities such as resting electrocardiogram (ECG), echocardiography (ECHO), or treadmill stress testing (TMT) are frequently insensitive to detect microvascular or vasospastic pathology, contributing to misdiagnosis [8]. Cardiac magnetic resonance (CMR) has emerged as a pivotal diagnostic tool combining stress perfusion imaging to detect perfusion deficits with late gadolinium enhancement sequences confirming ischemic injury [9].
The novelty of this series lies in highlighting the diagnostic journey of an adolescent and a young adult whose cardiac symptoms were initially overlooked. We emphasize the use of stress perfusion CMR and LGE sequences as the essential ‘keys’ to uncovering functional coronary disorders in a demographic typically considered low-risk by conventional standards.
Case Presentation
Case 1 the adolescent with an adult’s diagnosis
A 16-year-old male, previously healthy and physically active presented with sudden episodes of palpitations and left arm pain for a few hours. These were unprovoked, occurring at rest and occasionally accompanied by a brief, sharp chest discomfort. He had no history of hypertension, diabetes, smoking, obesity, or family history of premature coronary disease. His initial evaluations including physical examination, ECG, ECHO, and cardiac biomarkers were unremarkable. He was reassured and sent home with a low-dose beta-blocker.
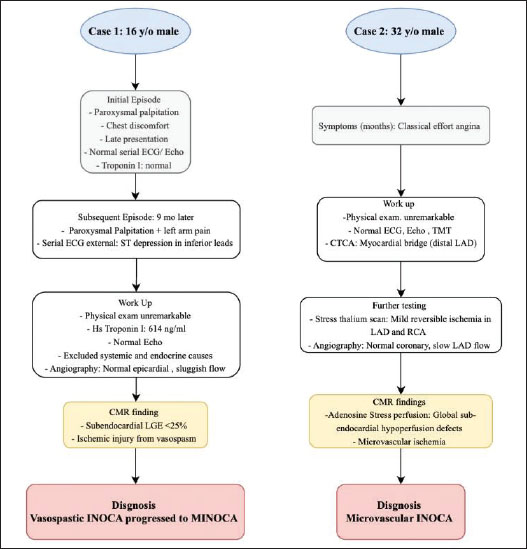
Figure 1. (A) ECG done at the time of symptoms showing sinus tachycardia and ST-T changes. (B) ECG done at Zydus hospital showing normal sinus rhythm and no significant ST-T changes.
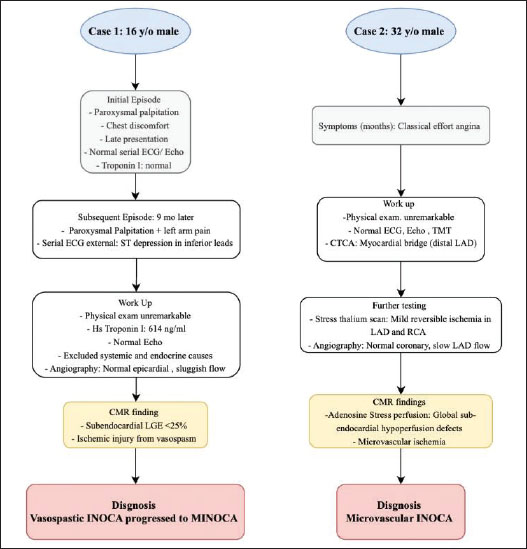
Figure 2. CAG of Case 1 (A) Dominant Left coronary artery system showing normal epicardial vessel (B) Non dominant normal Right coronary artery
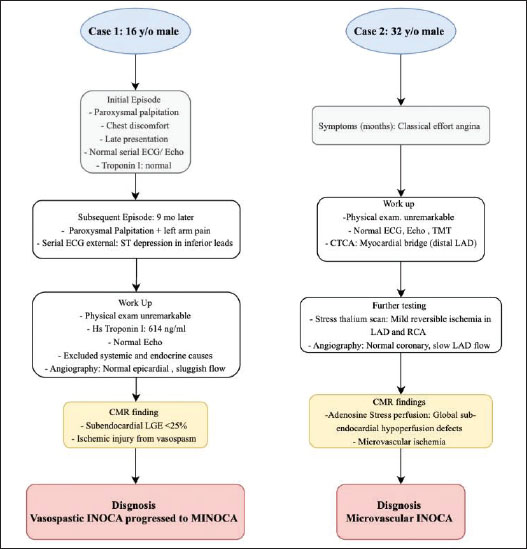
Figure 3. CMR-LGE images of Case 1. (A) Four-chamber and (B) three-chamber views demonstrate focal subendocardial enhancement (arrow) in the basal inferolateral wall. (C) Short-axis view showing focal subendocardial enhancement (arrow). (D) Four-chamber view with reference line correlating the short-axis slice location.
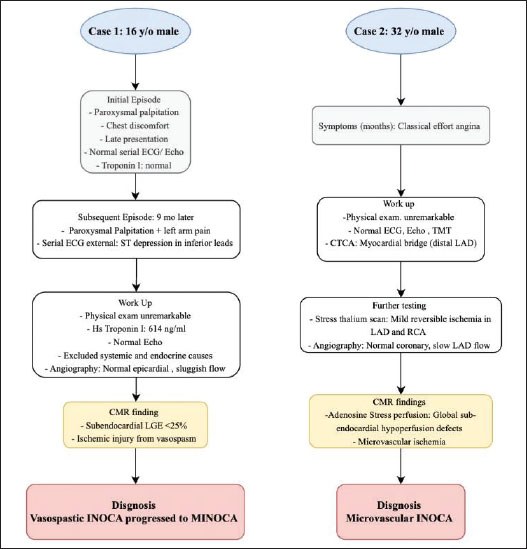
Figure 4. Case 2 ECG at the hospital showing NSR and no ST-T changes.
Nine months later, recurrent paroxysmal palpitations with left arm discomfort and chest pain at rest prompted readmission. The first of the serial ECGs obtained at symptom onset demonstrated sinus tachycardia with transient ST-segment depression in leads V4–V6 (Figure 1A). A subsequent ECG at our hospital showed normal sinus rhythm with no significant ST segment/ T wave changes (Figure 1B).
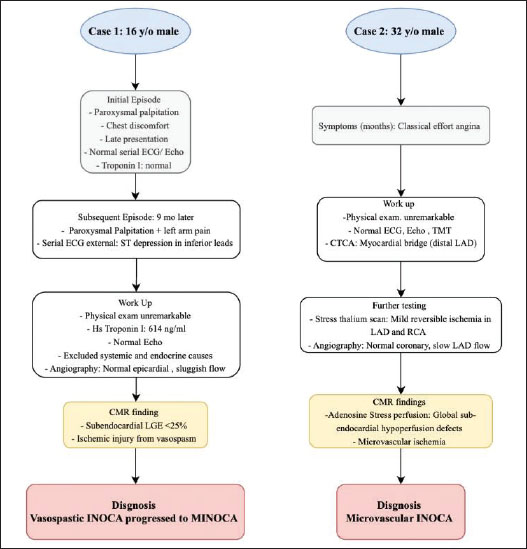
Figure 5. CAG of Case 2 (A) Left coronary system showing normal epicardial vessels (B) Dominant right coronary artery showing normal epicardial vessel.
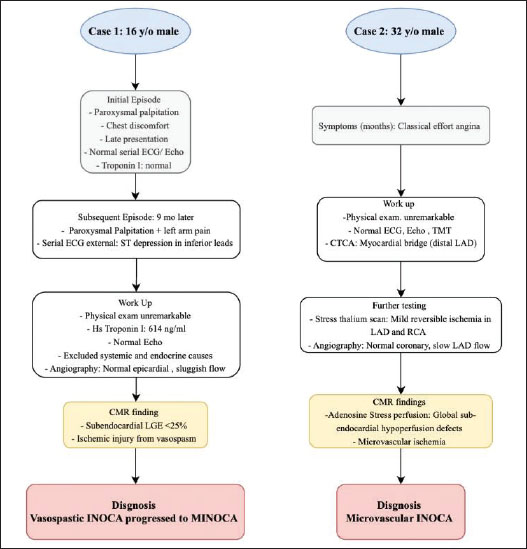
Figure 6. Stress perfusion cardiac magnetic resonance (CMR) in Case 2. (A) Short-axis stress perfusion imaging demonstrating a global subendocardial perfusion defect (arrows). (B) Quantitative perfusion mapping during stress revealed reduced myocardial blood flow (MBF 1.54 ml/min/g) and a mildly reduced myocardial perfusion reserve index (MPRI 2.04). (C) Rest perfusion imaging showed no fixed defects (arrow). (D) Rest perfusion mapping confirmed preserved myocardial blood flow (MBF 0.75 ml/min/g).
Laboratory investigations revealed elevated Troponin I of 0.871 ng/ml and High sensitivity troponin I of 614 ng/l (reference <14 ng/l). Physical examination showed blood pressure 133/76 mmHg and heart rate 83 beats per minute. ECHO confirmed preserved systolic function and no structural cardiac abnormalities.
Comprehensive laboratory workup excluded systemic inflammation (C-Reactive Protein normal), dyslipidemia (LDL 101 mg/dl, HDL 37 mg/dl, triglycerides 188 mg/dl), endocrine disorders, catecholamine-secreting tumors (plasma metanephrines negative) and hematological abnormalities.
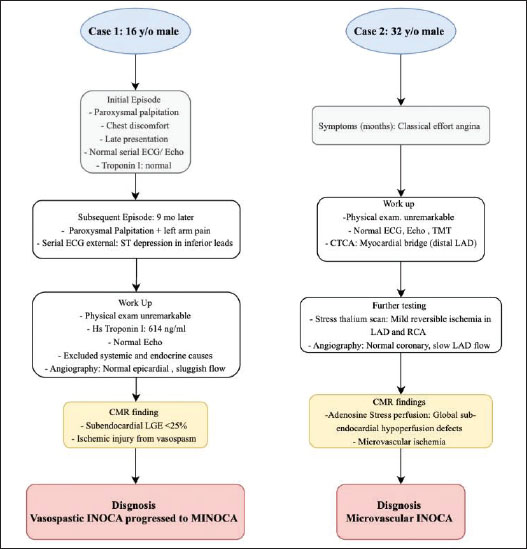
Figure 7. Flow chart summarizing the case series.
Coronary angiography was performed, which demonstrated normal epicardial vessels with diffusely sluggish flow (Figure 2).
In the absence of anatomical obstruction to explain the myocardial injury, the team moved to CMR for further evaluation, which showed good biventricular systolic function with normal chamber sizes, but revealed a focal area of subendocardial LGE in the basal inferolateral wall affecting less than 25% of the wall’s thickness Figure 3. This pattern confirmed a limited subendocardial myocardial infarction in the absence of obstructive coronary artery disease, supporting the diagnosis of MINOCA attributable epicardial or microvascular spasm. The patient was started on a calcium channel blocker, anti-anginal therapy, and antiplatelet agents. At the 6 months follow-up, the patient remains asymptomatic with no further anginal episodes and is doing well clinically.
Case 2 the young adult with invisible yet bothering angina
A 34-year-old physically active male without cardiovascular risk factors or family history of premature coronary artery disease, presented with a four-month history of classical angina which were characterized by exertional chest pain, dyspnea on exertion, and occasionally a sense of suffocation. Symptoms were reproducible with physical activity and resolved with rest.
Six weeks prior, a routine health evaluation included normal resting ECG, ECHO of ejection fraction 60%, no wall motion abnormalities, and normal TMT. At our hospital, a resting ECG again showed no abnormalities (Figure 4).
Laboratory investigations and high-sensitive troponin I were normal.
A computed tomography coronary angiography (CTCA) was performed which identified a minor myocardial bridge over the distal left anterior descending artery (LAD) with otherwise normal appearing coronary tree. Given the ongoing exertional symptoms, a stress myocardial perfusion imaging (MPI) revealed mild reversible ischemia in both the territories of left anterior descending and right coronary arteries.
Invasive coronary angiography demonstrated normal epicardial vessels with no obstructive lesions, but slow coronary flow in the LAD (TIMI 2 flow) (Figure 5).
To further investigate for microvascular ischemia, a stress cardiac magnetic resonance (CMR) imaging was performed (Figure 6) using adenosine infusion (140 mcg/kg/min) and gadolinium-based contrast. The study showed a mildly reduced LVEF (~53%) without RWMA. During stress, a uniform global subendocardial perfusion defect was observed in the left ventricle. Quantitative perfusion mapping demonstrated reduced stress myocardial blood flow (MBF 1.54 ml/min/g; Normal value 2.54 ml/min/g) and a mildly reduced myocardial perfusion reserve index (MPRI 2.04). LGE sequences showed no evidence of scar or fibrosis. Findings are consistent with global microvascular ischemia in the absence of obstructive epicardial disease, leading to a diagnosis of microvascular INOCA.
The patient was commenced on a diltiazem, nicorandil, ranolazine, trimetazidine, and atorvastatin. At 6 months follow up he remained asymptomatic.
Discussion
In adolescents, the rarity of atherosclerosis makes vasomotor dysfunction the leading cause of ischemia. Evidence of increased smooth-muscle reactivity and endothelial impairment in young patients suggests that coronary spasm is a likely mechanism of chest pain occurring at rest [5,10]. In chronic coronary syndromes, ischemia reflects an imbalance between coronary flow and myocardial demand.[4] Beyond obstructive disease, impaired microvascular dilation or inappropriate vasoconstriction can produce this mismatch, underscoring the need for mechanism-directed therapy [2,6].
These two cases illustrate distinct forms of ischemia without obstructive CAD Figure 7. The adolescent demonstrates epicardial vasospasm, transient and severe vasoconstriction driven by vascular smooth muscle hyperactivity, capable of causing myocardial necrosis. The focal subendocardial LGE on CMR confirmed limited myocardial injury from prolong vasospastic episode. In contrast, the young adult demonstrates CMD, specifically impaired by vasodilatory capacity of microcirculation, revealed by stress thallium and stress CMR. The small myocardial bridge identified in the distal LAD could not account for ischemia in the RCA territory, indicating that CMD was the primary driver [11].
These pathophysiologic distinctions mandated divergent management approaches. For the vasospastic MINOCA, therapy focused on preventing epicardial spasm through calcium channel blockers (diltiazem) as first-line treatment, supplemented by nicorandil as an additional antispastic agent. Conversely, for the microvascular INOCA, treatment targeted improving microvascular vasodilatory capacity and reducing myocardial oxygen demand. The multi-drug regimen included nicorandil (direct microvascular vasodilator), ranolazine (particularly effective in CMD with reduced CFR), and trimetazidine (metabolic modulator) [4].
While 6-month follow-up confirms sustained symptom resolution, the primary limitation remains the lack of long-term longitudinal data in this young cohort. Additionally, the specialized requirement for stress CMR with quantitative perfusion mapping may restrict generalizability in resource-constrained settings.
Nevertheless, the cases show that non-obstructive ischemia can range from microvascular-mediated angina to infarction and underscore the value of precision imaging. From a diagnostic perspective the cases emphasize the importance of a stepwise diagnostic approach: excluding obstructive disease, performing structured physiological assessment, and adopting advanced functional imaging to define ischemic mechanism [5]. This prevents unnecessary procedures and therapeutic under-treatment, associated with long term anxiety and poor quality of life [1]. While intracoronary acetylcholine testing remains the gold standard for diagnosing vasospasm in MINOCA [12], our experience demonstrates that advanced CMR provides a safe and informative alternative when invasive testing is not feasible.
Conclusion
These two cases challenge the assumption that myocardial ischemia is the domain of older patients with well-defined risk factors. INOCA can emerge quietly, in individuals at the peak of health, and remain invisible on routine testing until advanced imaging reveals its presence. Both presentations underscore a gap in clinical awareness: without considering vasospastic and microvascular mechanisms, patients may be reassured too soon, delaying diagnosis and leaving them vulnerable to ongoing ischemia and its potential complications. Ultimately, these cases demonstrate that the diagnostic ‘key’ for the young, symptomatic patient is the transition from anatomical assessment to functional characterization. By heightened awareness, informed suspicion, and early use of sensitive imaging we move past the common pitfall of ‘atypical’ labels and toward mechanism-specific care that can fundamentally change a patient’s cardiovascular trajectory.
What is new?
Young patients presenting with chest pain are often considered as non-cardiac particularly when basic conventional reports are normal. This case series highlights the importance of appropriate clinical history, detailed investigation and advanced imaging in finding out subtle yet clinically relevant and sometimes fatal cardiac conditions in these patients
List of abbreviations
| ACS | Acute Coronary Syndrome |
| ANOCA | Angina with Non-Obstructive Coronary Arteries |
| CAD | Coronary Artery Disease |
| CAG | Coronary Angiography |
| CAS | Coronary Artery Spasm |
| CBC | Complete Blood Count |
| CMD | Coronary Microvascular Dysfunction |
| CMR | Cardiac Magnetic Resonance |
| CRP | C-reactive Protein |
| CTCA | Computed Tomography Coronary Angiography |
| ECG | Electrocardiogram |
| ECHO | Echocardiography |
| HDL | High-Density Lipoprotein |
| INOCA | Ischemia with non-obstructive coronary arteries |
| LAD | Left Anterior Descending (artery) |
| LDL | Low-Density Lipoprotein |
| LGE | Late Gadolinium Enhancement |
| LVEF | Left Ventricular Ejection Fraction |
| MBF | Myocardial Blood Flow |
| MINOCA | Myocardial infarction with non-obstructive coronary arteries |
| MPI | Myocardial perfusion Imaging |
| MPRI | Myocardial Perfusion Reserve Index |
| MVA | Microvascular Angina |
| RCA | Right Coronary Artery |
| RWMA | Regional Wall Motion Abnormalities |
| TIMI | Thrombolysis In Myocardial Infarction (flow grade) |
| TMT | Treadmill Test |
| TSH | Thyroid Stimulating Hormone |
| VSA | Vasospastic angina |
Conflict of interest
The authors declare that there is no conflict of interest regarding the publication of this article.
Funding
None.
Consent for publication
Written informed consent was obtained from the patient /from the parents of the patient.
Ethical Approval
Ethical approval is not required at our institution to publish an anonymous case series.
Author details
Naqiya Arsiwala1, Abhisheka Tripathi2, Binal Raj3, Divyesh Dadhania4
- Medical Student, School of Medicine and Surgery, Università Cattolica Del Sacro Cuore, Rome, Italy
- Department of Cardiology, Zydus Hospitals and Healthcare Research Private Limited, Ahmedabad, India
- Clinical Cardiology Associate, Department of Cardiology, Ahmedabad, Zydus Hospitals and Healthcare Research Private Limited, India.
- Cardiovascular Imaging, Department of Interventional Radiology, Zydus Hospitals and Healthcare Research Private Limited, Ahmedabad, India
References
- Jespersen L, Abildstrøm SZ, Hvelplund A, Prescott E. Persistent angina: highly prevalent and associated with long-term anxiety, depression, low physical functioning, and quality of life in stable angina pectoris. Clin Res Cardiol. 2013;102(8):571–81. https://doi.org/10.1007/s00392-013-0568-z
- Ford TJ, Stanley B, Good R, Rocchiccioli P, McEntegart M, Watkins S, et al. Stratified medical therapy using invasive coronary function testing in angina: the CorMicA trial. J Am Coll Cardiol. 2018;72(23 Pt A 24Pt A):2841–55. https://doi.org/10.1016/j.jacc.2018.09.006
- Parlati AL, Nardi E, Sucato V, Madaudo C, Leo G, Rajah T, et al. ANOCA, INOCA, MINOCA: the New Frontier of Coronary Syndromes. J Cardiovasc Dev Dis. 2025;12(2):64. https://doi.org/10.3390/jcdd12020064
- Vrints C, Andreotti F, Koskinas KC, Rossello X, Adamo M, Ainslie J, et al. 2024 ESC Guidelines for the management of chronic coronary syndromes. Eur Heart J. 2024;45(36):3415–537.
- Kunadian V, Chieffo A, Camici PG, Berry C, Escaned J, Maas AHEM, et al. An EAPCI Expert Consensus Document on Ischaemia with Non-Obstructive Coronary Arteries (INOCA) in collaboration with the European Society of Cardiology Working Group on Coronary Pathophysiology & Microcirculation. Eur Heart J. 2020;41(37):3504–20. https://doi.org/10.1093/eurheartj/ehaa503
- Bairey Merz CN, Pepine CJ, Walsh MN, Fleg JL, Camici PG, Chilian WM, et al. Ischemia and no obstructive coronary artery disease (INOCA): developing evidence-based therapies and research agenda for the next decade. Circulation. 2017;135(11):1075–92. https://doi.org/10.1161/CIRCULATIONAHA.116.024534
- Tamis-Holland JE, Jneid H, Reynolds HR, Agewall S, Brilakis ES, Brown TM, et al. Contemporary diagnosis and management of patients with myocardial infarction in the absence of obstructive coronary artery disease: a scientific statement from the American Heart Association. Circulation. 2019;139(18):e891–908. https://doi.org/10.1161/CIR.0000000000000670
- Ford TJ, Berry C. Angina: contemporary diagnosis and management. Heart. 2020;106(5):387–98. https://doi.org/10.1136/heartjnl-2018-314661
- Zhou W, Lee JCY, Leung ST, Lai A, Lee TF, Chiang JB, et al. Long-term prognosis of patients with coronary microvascular disease using stress perfusion cardiac magnetic resonance. JACC Cardiovasc Imag. 2021;14(3):602–11. https://doi.org/10.1016/j.jcmg.2020.09.034
- Yaker ZS, Lincoff AM, Cho L, Ellis SG, Ziada KM, Zieminski JJ, et al. Coronary spasm and vasomotor dysfunction as a cause of MINOCA. EuroIntervention. 2025;21(3):e271–282.
- Tarantini G, Migliore F, Cademartiri F, Fraccaro C, Iliceto S. Left anterior descending artery myocardial bridging: a clinical approach. J Am Coll Cardiol. 2016;68(25):2887–999. https://doi.org/10.1016/j.jacc.2016.09.973
- Montone RA, Niccoli G, Fracassi F, Russo M, Gurgoglione F, Cammà G, et al. Patients with acute myocardial infarction and non-obstructive coronary arteries: safety and prognostic relevance of invasive coronary provocative tests. Eur Heart J. 2020;41(15):1285–96.
Summary of the case
| 1 | Patient (gender, age) | 16y/o male and 34 y/o male |
| 2 | Final diagnosis | Ischemia with non-obstructive coronary arteries |
| 3 | Symptoms | Paroxysmal palpitation and chest Discomfort |
| 4 | Medications | Symptomatic treatment given |
| 5 | Clinical procedure | Echo, TMT, CAG, Stress thallium scan, CMR |
| 6 | Specialty | Cardiology |
Keywords: INOCA/MINOCA, cardiac MRI, vasomotor dysfunction, vasospastic angina, young patients.


Publication History
Received: November 20, 2025
Revised: February 16, 2026
Accepted: March 04, 2026
Published: April 13, 2026
Authors
Naqiya Arsiwala
Medical Student, School of Medicine and Surgery, Università Cattolica Del Sacro Cuore, Rome, Italy.
 ORCID
Abhisheka Tripathi
Department of Cardiology, Zydus Hospitals and Healthcare Research Private Limited, Ahmedabad, India.
Binal Raj
Clinical Cardiology Associate, Department of Cardiology, Ahmedabad, Zydus Hospitals and Healthcare Research Private Limited, India.
Divyesh Dadhania
Cardiovascular Imaging, Department of Interventional Radiology, Zydus Hospitals and Healthcare Research Private Limited, Ahmedabad, India.