European Journal of Medical Case Reports
Volume 10(8):273–276
Polycythemia vera: a catastrophic hemorrhagic complication – a case report
Ana Filipa Coimbra Trigo1* , Ana Rita Ramos1, Marcia Melo2
Correspondence to: Ana Filipa Coimbra Trigo
*Department of Nephrology, Unidade Local de Saude do Medio Tejo, Tomar, Portugal.
Email: anatrigo_347@hotmail.com
Full list of author information is available at the end of the article.
Received: 15 December 2025 | Revised (1): 10 February 2026 | Accepted:12 March 2026
ABSTRACT
Background:
One of the main goals of treatment in polycythemia vera (PV) is the prevention of arterial and venous thrombosis. However, less commonly, patients may also experience hemorrhagic events. This case report aims to raise awareness of these complications. We describe a patient with PV who developed a non-traumatic subdural hematoma (SDH) - a rare presentation - with severe impact on life expectancy.
Case Presentation:
A 53-year-old man, diagnosed with PV at the age of 46, presented to the emergency department with right arm weakness, which progressed to right leg weakness and dysarthria. Computed tomography revealed a large acute interhemispheric SDH requiring craniotomy. During hospitalization, the patient had persistent leukocytosis above 16 × 10⁹/l. He did not recover consciousness and was discharged with a Glasgow Coma Scale score of 9.
Conclusion:
Hemorrhagic complications in PV may result from antiplatelet or anticoagulant therapy, acquired Von Willebrand Syndrome, or platelet dysfunction. Additional risk factors include age at diagnosis, disease duration, prior bleeding, and leukocytosis (particularly >16 × 10⁹/l). Our patient presented multiple risk factors for bleeding. Earlier recognition of hemorrhagic risk might have prompted consideration of alternative management strategies; however, it remains uncertain whether this would have altered the clinical outcome. This case highlights the importance of considering hemorrhagic complications, in addition to thrombosis prevention, in patients with PV.
Keywords:
Myeloproliferative disorders, polycythemia vera, hematoma, subdural, acute.
Introduction
Polycythemia vera (PV) is a myeloproliferative disorder caused by a somatic mutation in a single hematopoietic stem cell, leading to clonal hematopoiesis [1]. In most cases, the disease is associated with the JAK2 V617F mutation, resulting in increased red blood cell production. Erythrocytosis is the defining feature that distinguishes PV from other myeloproliferative disorders [2].
The main clinical manifestations of PV include pruritus, palpable splenomegaly, and vasomotor symptoms. According to published data, the most common post-diagnosis complications are arterial and venous thrombosis, occurring in approximately 12% and 9% of patients, respectively. Major hemorrhagic events may also occur, although less frequently, with a reported incidence of about 4.2% [3]. Consequently, standard PV management includes acetylsalicylic acid to reduce thrombotic risk, which may lead to underestimation of the associated hemorrhagic risk. Identifying patients at increased risk of bleeding remains challenging in clinical practice, but it is crucial in their management.
Head trauma is the leading cause of subdural hematoma (SDH), with non-traumatic cases accounting for approximately 29% of all SDHs. The main non-traumatic etiologies include rupture of an intracranial aneurysm or cortical artery, hypertensive intracerebral hemorrhage, neoplasms, hematologic disorders, anticoagulant or thrombolytic therapy, cerebral amyloid angiopathy, dural arteriovenous fistula, and acquired immunodeficiency syndrome [4].
Non-traumatic SDH is an exceptionally rare manifestation in patients with PV, with very few cases reported in the literature. In this case report, we describe the coexistence of two rare events: a non-traumatic SDH as a hemorrhagic complication in a patient with PV and no other identifiable risk factors. This outcome had a profound impact on the patient’s prognosis and life expectancy, underscoring the need to raise clinical awareness of hemorrhagic complications in PV.
Case Presentation
A 53-year-old man diagnosed with PV in 2014, positive for the JAK2 V617F mutation, presented to the emergency department in January 2021 with right arm weakness that had begun earlier that day. He denied any history of head trauma, motor vehicle accident, or head injury. During physical examination, the weakness progressed to the right leg, and he developed dysarthria. His vital signs were: temperature 36°C, blood pressure 128/76 mmHg, and heart rate 75 beats/min.
Before completion of the diagnostic workup, the patient developed rapid neurological deterioration and sudden respiratory failure requiring endotracheal intubation, with a Glasgow Coma Scale (GCS) score of 3. The absence of head trauma or recent injury was later confirmed by family members.
Computed tomography (CT) revealed a large acute interhemispheric subdural hematoma (ISDH) with rightward midline shift (Figure 1). CT angiography showed no vascular abnormalities. Laboratory results at admission are summarized in Table 1. Urinalysis and renal function were normal, and C-reactive protein levels were within normal limits.
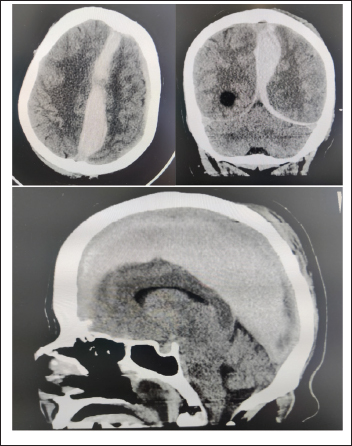
Figure 1. Preoperative CT scan images revealing an ISDH with 20 mm maximal thickness in the coronal plane, conditioning a 22.13 mm midline shift to the right.
Table 1. Laboratory values at admission.
| PATIENT NORMAL | VALUES | |
|---|---|---|
| Leukocytes | 28.18 × 10⁹/l | 4.0-10.0 ×10⁹/l |
| Neutrophiles | 26.12 ×10⁹/l (92%) | 1.5-7.0 ×10⁹/l (37.0%-72.0%) |
| Hemoglobin | 14.0 g/dl | 12.5-15.5 g/dl |
| Hematocrit | 48.8% | 40.0%-50.0% |
| Platelets | 417 ×109/l | 140-400 ×109/l |
| PT | 14.10 seconds | 9.0-13.0 seconds |
| aPTT | 30.5 seconds | 23-32 seconds |
| INR | 1.34 | |
| Alkaline phosphatase | 138 IU/l | 30-120 IU/l |
| GGT | 76 IU/l | 0-55 IU/l |
| AST | 39 U/l | 0-50 U/l |
| ALT | 54 U/l | 0-50 U/l |
PT, Prothrombin Time; aPTT, activated Partial Thromboplastin Time; INR, International Normalized Ratio; GGT, Gamma-Glutamyltransferase; AST, Aspartate transaminase; ALT, alanine aminotransferase.
Regarding his past medical history, the patient was enrolled in a chronic phlebotomy program, with the last session performed in October 2020. He had been receiving acetylsalicylic acid 100 mg daily and hydroxyurea 500 mg daily since diagnosis. An abdominal ultrasound performed in November 2020 showed mild, homogeneous splenomegaly. He also had a history of hypertension, well controlled with losartan; blood pressure measurements during follow-up over the previous 3 years ranged from 128/70 to 142/83 mmHg. He had no prior history of arterial or venous thrombosis; however, an episode of hematuria had occurred 3 months before the hemorrhagic event, which may represent an early manifestation of bleeding tendency rather than a direct precipitating factor.
The patient underwent emergent craniotomy with evacuation of the hematoma. Postoperatively, he was admitted to the neurosurgical intensive care unit, where recovery of consciousness was minimal, and a tracheostomy was required. During hospitalization, persistent leukocytosis was observed. Platelet counts exceeded 1 × 10⁶/µl on one occasion, prompting evaluation for acquired Von Willebrand Syndrome (aVWS), which was negative, but not leading to immediate changes in cytoreductive therapy. He was subsequently transferred to an internal medicine ward and discharged with a GCS score of 9.
Other secondary causes of SDH, including vascular malformations, non-PV-related coagulopathies, and medication-related causes, were reasonably excluded after review of imaging, laboratory results, and clinical history.
Discussion
Non-traumatic SDH is associated with high morbidity and mortality, particularly in patients presenting with severe neurological impairment, making the poor neurological outcome observed in this case consistent with published prognostic data. [4]
Hemorrhage in PV may result from antiplatelet or anticoagulant therapy, aVWS, or intrinsic platelet dysfunction [2]. aVWS is a bleeding disorder secondary to lymphoproliferative and myeloproliferative diseases, most commonly essential thrombocythemia; however, PV has also been associated with aVWS in up to 12% of cases, particularly in patients diagnosed at a younger age or with poor response to treatment [5]. Our patient was diagnosed at the age of 46 and showed disease progression with increasing leukocytosis. Although aVWS was not confirmed, evaluation was performed after the hemorrhagic event, and the possibility of intermittent or transient aVWS cannot be entirely excluded, particularly given the limitations of testing outside the acute phase.
Additional risk factors for bleeding in PV include prior bleeding history and leukocytosis, particularly values exceeding 16 × 109/l [2]. It remains unclear whether leukocytosis directly contributes to hemorrhagic risk through platelet–endothelial interactions or whether it merely reflects disease activity. Our patient had a prior bleeding episode (hematuria) and marked leukocytosis of 28.18 × 10⁹/l at admission, which had been sustained above 16 × 109/l for at least 9 months prior to the event. These factors have been associated with an increased risk of hemorrhagic events in observational studies, although a direct causal relationship cannot be definitively established.
Hydroxyurea is the first-line cytoreductive therapy for high-risk PV and has been consistently shown to reduce the incidence of arterial and venous thrombotic events through effective control of myeloproliferation and blood viscosity [6]. Importantly, hydroxyurea is not directly associated with an increased risk of major hemorrhagic complications [6]. In the present case, the occurrence of a severe hemorrhagic event in the setting of persistent leukocytosis suggests ongoing disease activity despite therapy, rather than a deleterious effect of hydroxyurea itself. This underscores the importance of regular reassessment of cytoreductive efficacy and consideration of treatment intensification or alternative agents in patients with suboptimal hematologic control.
Regarding acetylsalicylic acid, it was prescribed in accordance with guideline-based recommendations for thrombotic risk reduction in patients with PV. While low-dose aspirin has well-established benefits in reducing arterial thrombotic events in PV, it may also increase bleeding risk, particularly in patients with evolving disease characteristics such as prior bleeding or rising leukocyte counts. The balance between thrombotic prevention and hemorrhagic risk, therefore, requires individualized and dynamic reassessment. Importantly, it remains uncertain whether withholding aspirin before the event would have altered the clinical outcome in this case. This report is limited by its single-case design and short-term outcome assessment, which preclude definitive conclusions regarding causality or optimal management strategies.
Finally, it is important to recognize that major non-traumatic hemorrhage may represent the initial presentation of PV. Therefore, this diagnosis should be considered in patients presenting with non-traumatic intracranial hemorrhage without an obvious cause.
Conclusion
PV is associated with both thrombotic and hemorrhagic complications, the latter being less frequent but potentially devastating. This case highlights non-traumatic SDH as a rare hemorrhagic manifestation of PV and underscores the importance of careful and individualized assessment of bleeding risk. Early recognition of predisposing factors, such as prior bleeding and persistent leukocytosis, may allow timely reassessment of therapy, although its impact on outcomes in individual cases remains uncertain.
What is new
PV is not only a thrombotic disease. Severe non-traumatic intracranial hemorrhage may occur and profoundly affect prognosis. Close clinical monitoring and ongoing reassessment of hemorrhagic risk factors should be considered as part of therapeutic decision-making in patients with PV.
List of Abbreviations
| aVWS | Acquired Von Willebrand Syndrome |
| CT | Computed tomography |
| GCS | Glasgow Coma Scale |
| ISDH | Interhemispheric Subdural Hematoma |
| PV | Polycythemia Vera |
| SDH | Subdural Hematoma |
Acknowledgment
No acknowledges to declare.
Conflict of interests
The authors declare that there is no conflict of interest regarding the publication of this article.
Funding
None.
Consent for publication
Written informed consent was obtained from the next kin (brother) of the patient.
Ethical approval
Ethical approval is not required at our institution to publish an anonymous case report.
Declarations
Nothing to declare.
Author details
Ana Filipa Coimbra Trigo1, Ana Rita Ramos1, Marcia Melo2
- Department of Nephrology, Unidade Local de Saude do Medio Tejo, Tomar, Portugal
- Department of Internal Medicine, Unidade Local de Saude do Medio Tejo, Tomar, Portugal
References
- Prchal JT. Polycythemia vera and other primary polycythemias. Curr Opin Hematol. 2005;12(2):112–6. https://doi.org/10.1097/01.moh.0000154029.05396.d2
- Chou YS, Gau JP, Yu YB, Pai JT, Hsiao LT, Liu JH, et al. Leukocytosis in polycythemia vera and splenomegaly in essential thrombocythemia are independent risk factors for hemorrhage. Eur J Haematol. 2013;90(3):228–36. https://doi.org/10.1111/ejh.12064
- Tefferi A, Rumi E, Finazzi G, Gisslinger H, Vannucchi AM, Rodeghiero F, et al. Survival and prognosis among 1545 patients with contemporary polycythemia vera: an international study. Leukemia. 2013;27(9):1874–81. https://doi.org/10.1038/leu.2013.163
- Vega RA, Valadka AB. Natural history of acute subdural hematoma. Neurosurg Clin N Am. 2016;16:1042–3680.
- Mital A, Prejzner W, Świątkowska-Stodulska R, Hellmann A. Factors predisposing to acquired von Willebrand syndrome during the course of polycythemia vera - retrospective analysis of 142 consecutive cases. Thromb Res. 2015;136(4):754–7. https://doi.org/10.1016/j.thromres.2015.07.029
- Marchioli R, Finazzi G, Specchia G, Cacciola R, Cavazzina R, Cilloni D; CYTO-PV Collaborative Group, et al. Cardiovascular events and intensity of treatment in polycythemia vera. N Engl J Med. 2013;368(1):22–33. https://doi.org/10.1056/NEJMoa1208500
Summary of the case
| 1 | Patient (gender, age) | 53 years, male |
| 2 | Final diagnosis | Non-traumatic ISDH in a patient with polycythemia vera |
| 3 | Symptoms | Right arm weakness progressing to right leg weakness and dysarthria |
| 4 | Medications | Prior on: Acetylsalicylic acid, hydroxyurea; chronic phlebotomy program |
| 5 | Clinical procedure | Emergency craniotomy and evacuation of SDH; intensive care management |
| 6 | Specialty | Internal medicine/Hematology/Neurosurgery |
Keywords: Myeloproliferative disorders, polycythemia vera, hematoma, subdural, acute.


Publication History
Received: November 15, 2025
Revised: February 10, 2026
Accepted: March 12, 2026
Published: July 25, 2026
Authors
Ana Filipa Coimbra Trigo
Department of Nephrology, Unidade Local de Saude do Medio Tejo, Tomar, Portugal.
 ORCID
Ana Rita Ramos
Department of Nephrology, Unidade Local de Saude do Medio Tejo, Tomar, Portugal.
Márcia Melo
Department of Internal Medicine, Unidade Local de Saude do Medio Tejo, Tomar, Portugal.